

The landscape of American healthcare is currently undergoing a seismic shift as the federal government and individual states navigate a complex transition in Medicaid policy. At the heart of this transformation are Section 1115 demonstration waivers—a powerful regulatory tool that allows states to bypass federal Medicaid statutes to test innovative, and often controversial, approaches to public health coverage.
n
As the Trump administration moves to rescind Biden-era guidance focused on social determinants of health and continuous eligibility, a new era of Medicaid is emerging. This era is defined by the federal mandate of work requirements, a tightening of fiscal flexibility, and a re-evaluation of what it means to "promote the objectives" of the nation’s largest health insurer for low-income individuals.
n
Main Facts: The Regulatory Engine of Medicaid Innovation
n
Section 1115 of the Social Security Act grants the Secretary of Health and Human Services (HHS) the authority to waive certain provisions of the Medicaid law for "experimental, pilot, or demonstration" projects. In theory, these waivers must be budget-neutral to the federal government and must align with the core objectives of the Medicaid program. In practice, they have become the primary vehicle through which presidential administrations signal their healthcare priorities.
n
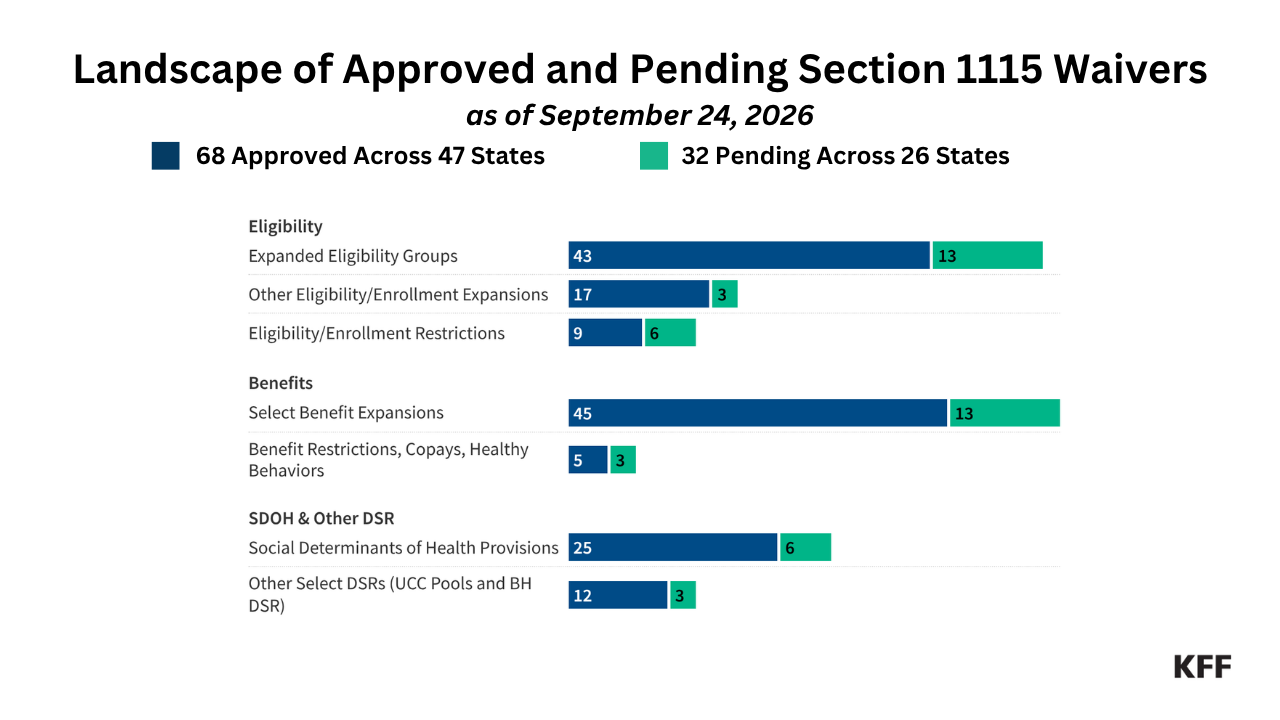
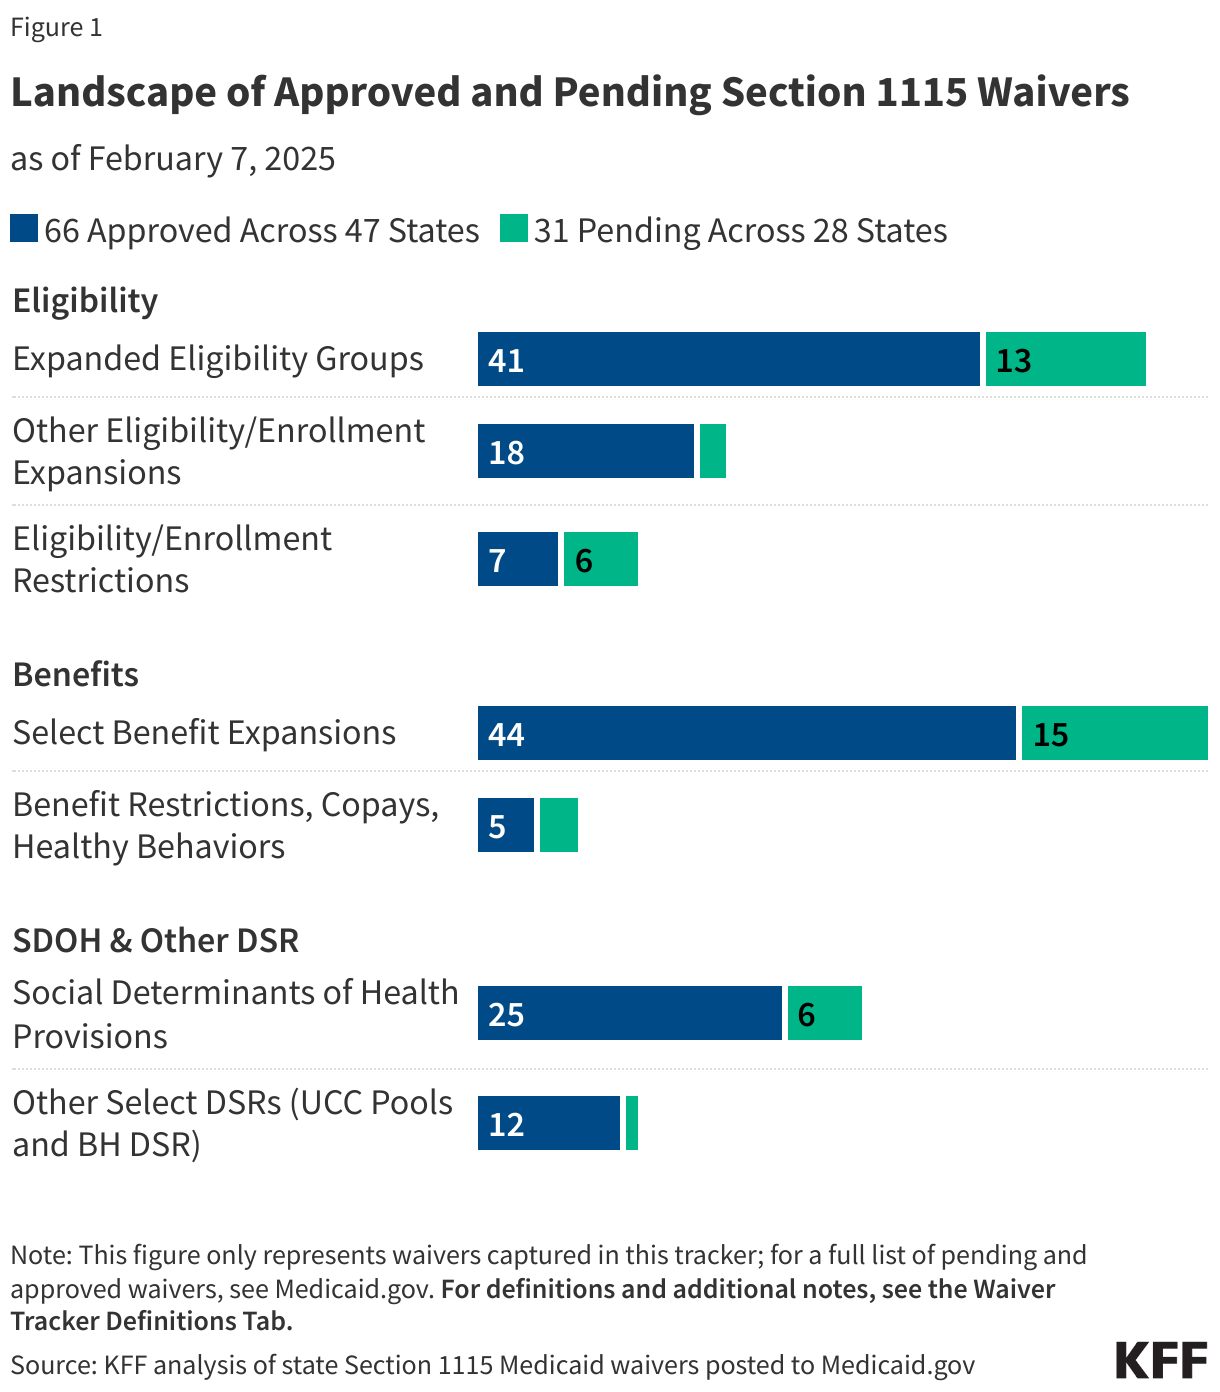
Currently, nearly every state in the U.S. operates at least one Section 1115 waiver. These demonstrations cover a vast array of policy areas, including eligibility expansions, benefit modifications, and delivery system reforms. However, the focus of these waivers is shifting rapidly. While the Biden-Harris administration utilized Section 1115 to address "Health-Related Social Needs" (HRSN)—such as housing and nutrition—the current administration is pivoting back to a philosophy of personal responsibility and workforce participation.
n
The most significant development in this space is the 2025 reconciliation law, which fundamentally changes the Medicaid expansion landscape. Starting January 1, 2027, states will be required to condition Medicaid eligibility for adults in the Affordable Care Act (ACA) expansion group on meeting specific work requirements. This federal mandate marks a departure from previous years, where work requirements were largely a state-led initiative pursued through individual waivers.
n
Chronology: A Rapid Reversal of Federal Priorities
n
To understand the current state of Medicaid, one must look at the rapid succession of policy changes that have occurred since the start of 2025. The transition between administrations has resulted in a "regulatory whiplash" for state Medicaid directors.
n
- n
- The Biden Era (2021–2024): The focus was on expanding the "whole-person" care model. CMS approved 19 state waivers to facilitate reentry for incarcerated individuals and 9 waivers for multi-year continuous eligibility for children. The administration also established a formal framework for addressing social determinants of health (SDOH).
- March 2025: The Trump administration rescinded the Biden-era HRSN guidance. While existing approvals were not immediately nullified, CMS announced that all future requests regarding social determinants would be handled on a case-by-case basis, effectively chilling new state applications in this category.
- April 2025: The administration announced the phasing out of federal funding for "Designated State Health Programs" (DSHP). This move targeted a common waiver mechanism states used to secure federal matching funds for existing state-funded health initiatives.
- July 2025: Two major blows to enrollment stability were delivered. CMS released guidance indicating it would no longer approve or extend continuous eligibility waivers for children or adults. Simultaneously, the administration began phasing out initiatives aimed at strengthening the Medicaid workforce in primary care and behavioral health.
- September 2026: In a rare moment of continuity, the administration approved four reentry waivers for incarcerated individuals but signaled that updated, more restrictive guidance for these "justice-involved" demonstrations would be released within the year.
- January 2027: The ultimate deadline. All states must come into compliance with federal work requirements for the ACA expansion population.
n
n
n
n
n
n
n
Supporting Data: States Leading the Charge on Work Requirements
n
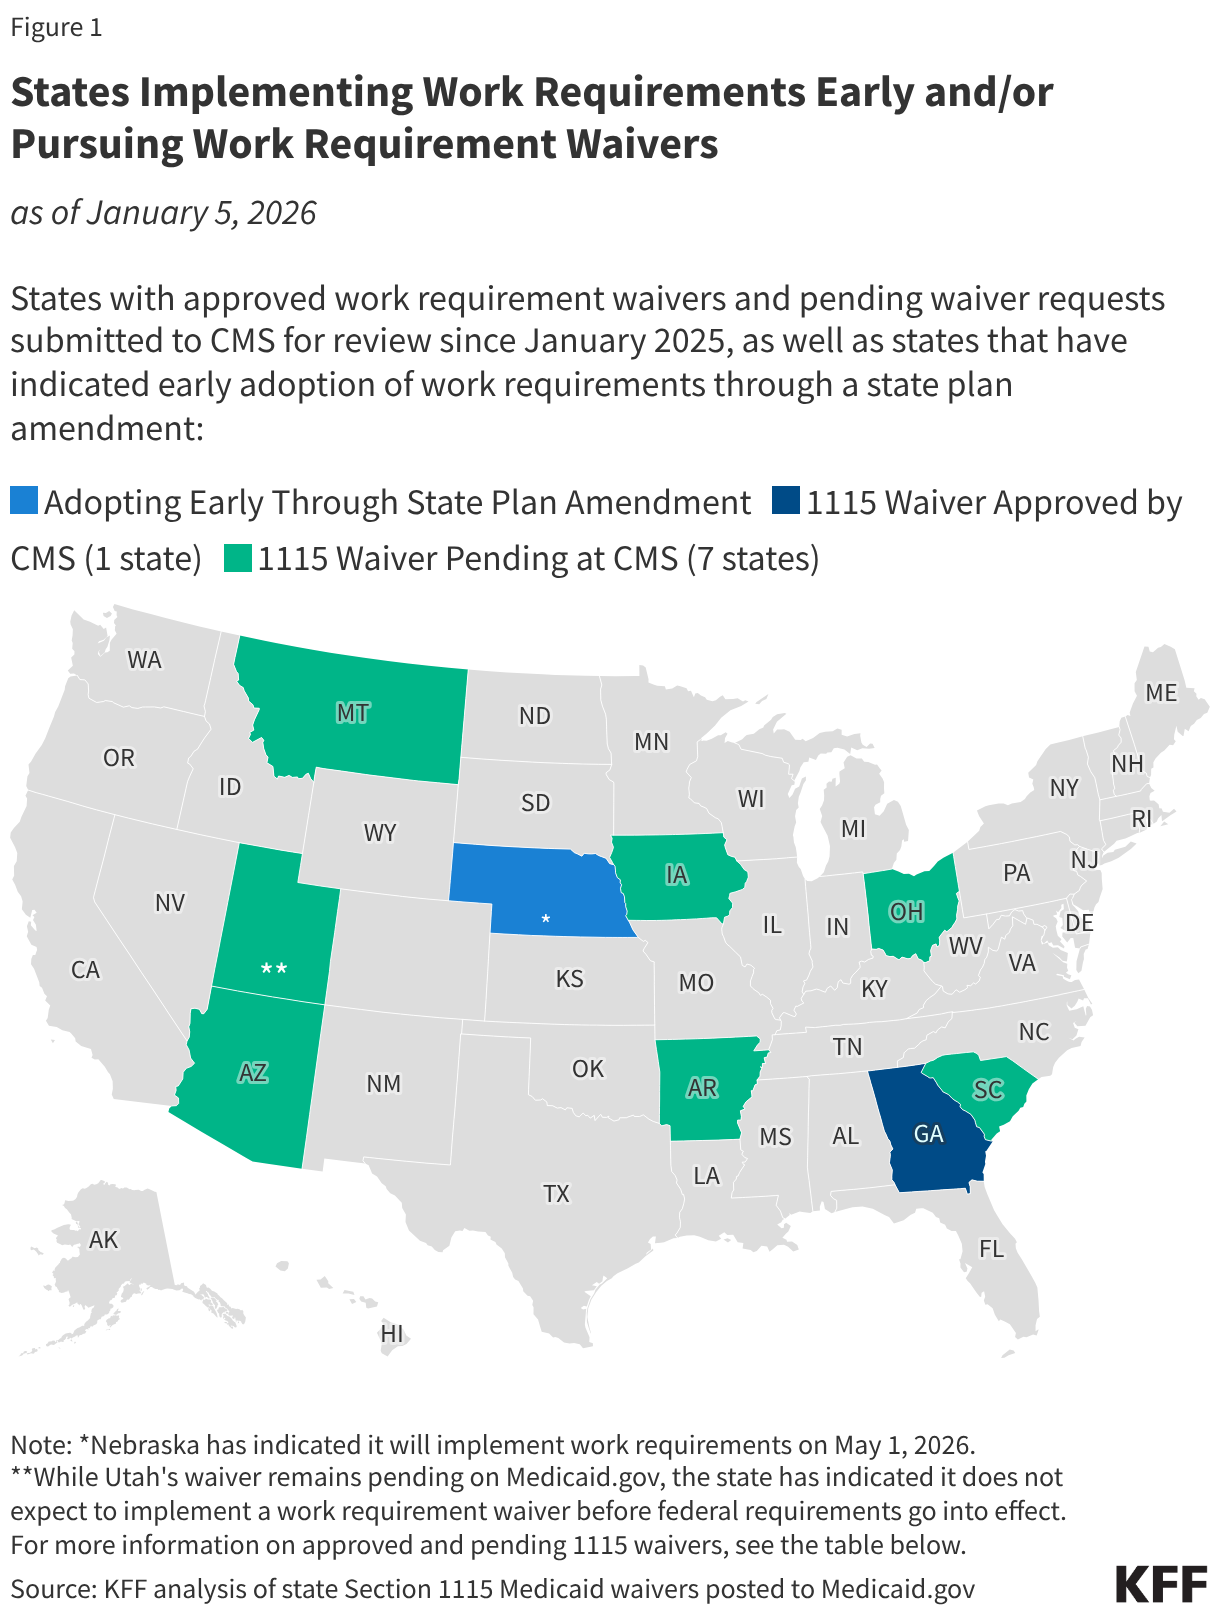
While the 2027 deadline is the "hard" target, several states are moving to implement work requirements much sooner through State Plan Amendments (SPAs) or existing waivers.
n
Early Adopters of Work Mandates
n
Nebraska has emerged as the vanguard of this movement, announcing it will begin enforcing federal work requirements as early as May 1, 2026. Following closely behind are Montana (July 1, 2026) and Iowa (December 1, 2026). Arkansas, a state with a long history of pursuing work mandates, has opted for a "soft implementation" starting in July 2026, where requirements are tracked but individuals are not disenrolled until the federal deadline in 2027.
n
The Georgia Exception
n
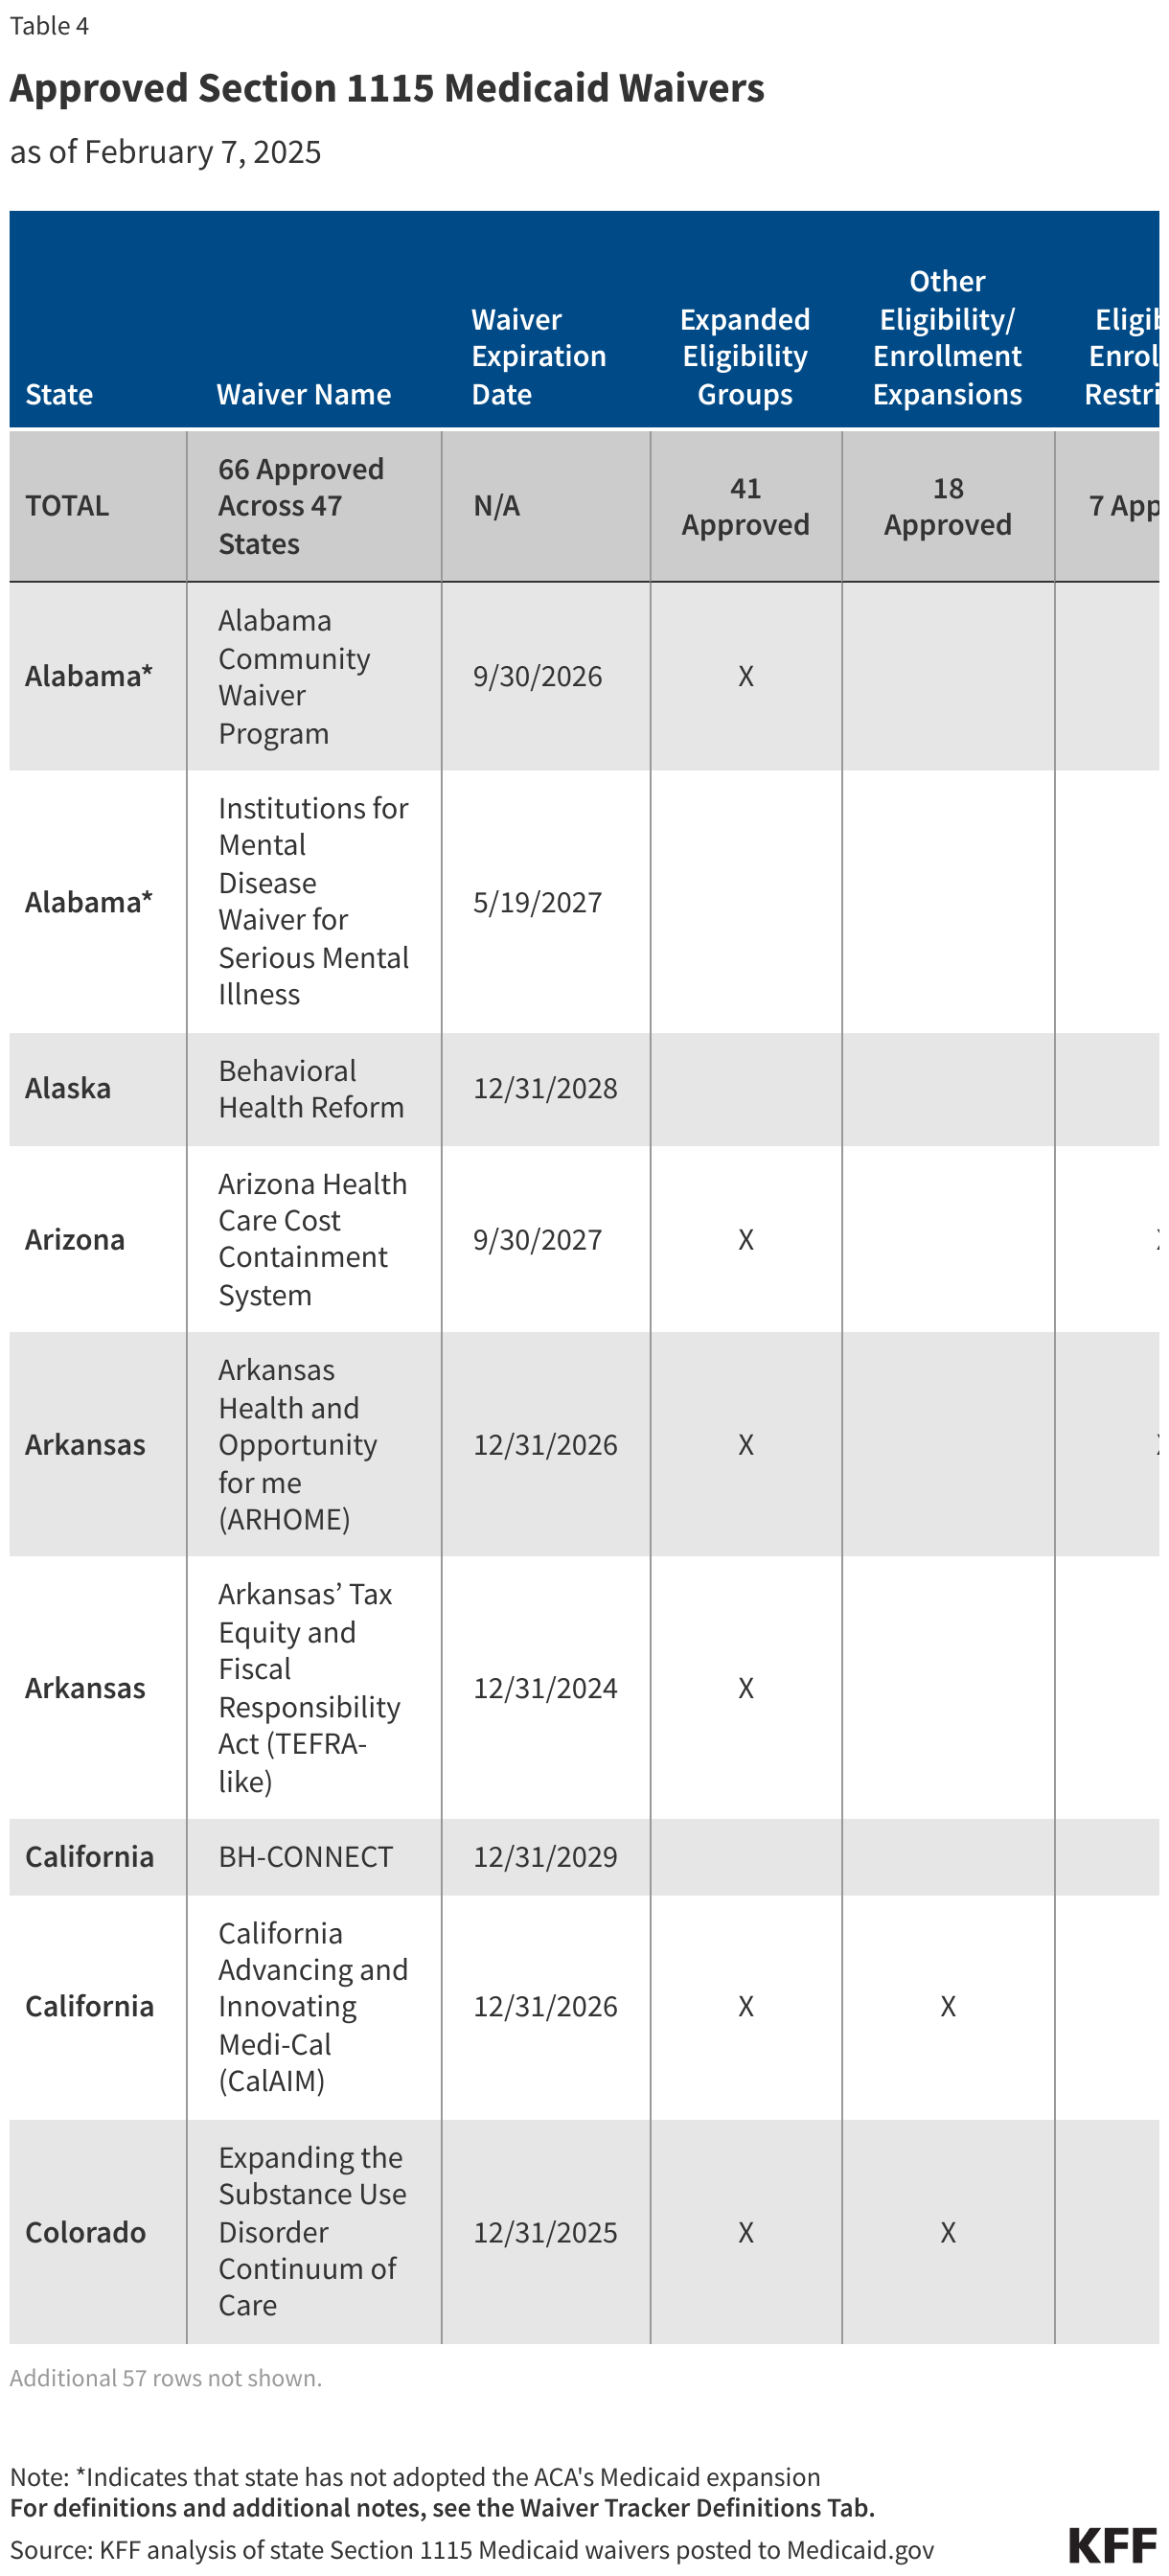
Georgia remains a unique case in the national landscape. It is currently the only state with an active, approved Medicaid work requirement waiver (Georgia Pathways to Coverage) that survived litigation during the Biden administration. However, Georgia’s specific waiver is set to expire on December 31, 2026. At that point, the state will have to transition from its custom waiver to the new federal standards mandated by the 2025 reconciliation law.
n
The Decline of Continuous Eligibility
n
One of the most praised policies of the pandemic era was "continuous eligibility," which prevents "churn"—the process where low-income individuals fluctuate in and out of Medicaid eligibility due to minor income changes or administrative hurdles.
n
Before the July 2025 rescission, nine states had received approval to provide multi-year continuous eligibility for children (often from birth to age six). Data from MACPAC and KFF has consistently shown that continuous coverage reduces administrative costs and improves health outcomes by ensuring uninterrupted care. The current administration’s decision to end these waivers represents a major shift toward "eligibility integrity" over "coverage continuity."
n
Official Responses: A Clash of Philosophies
n
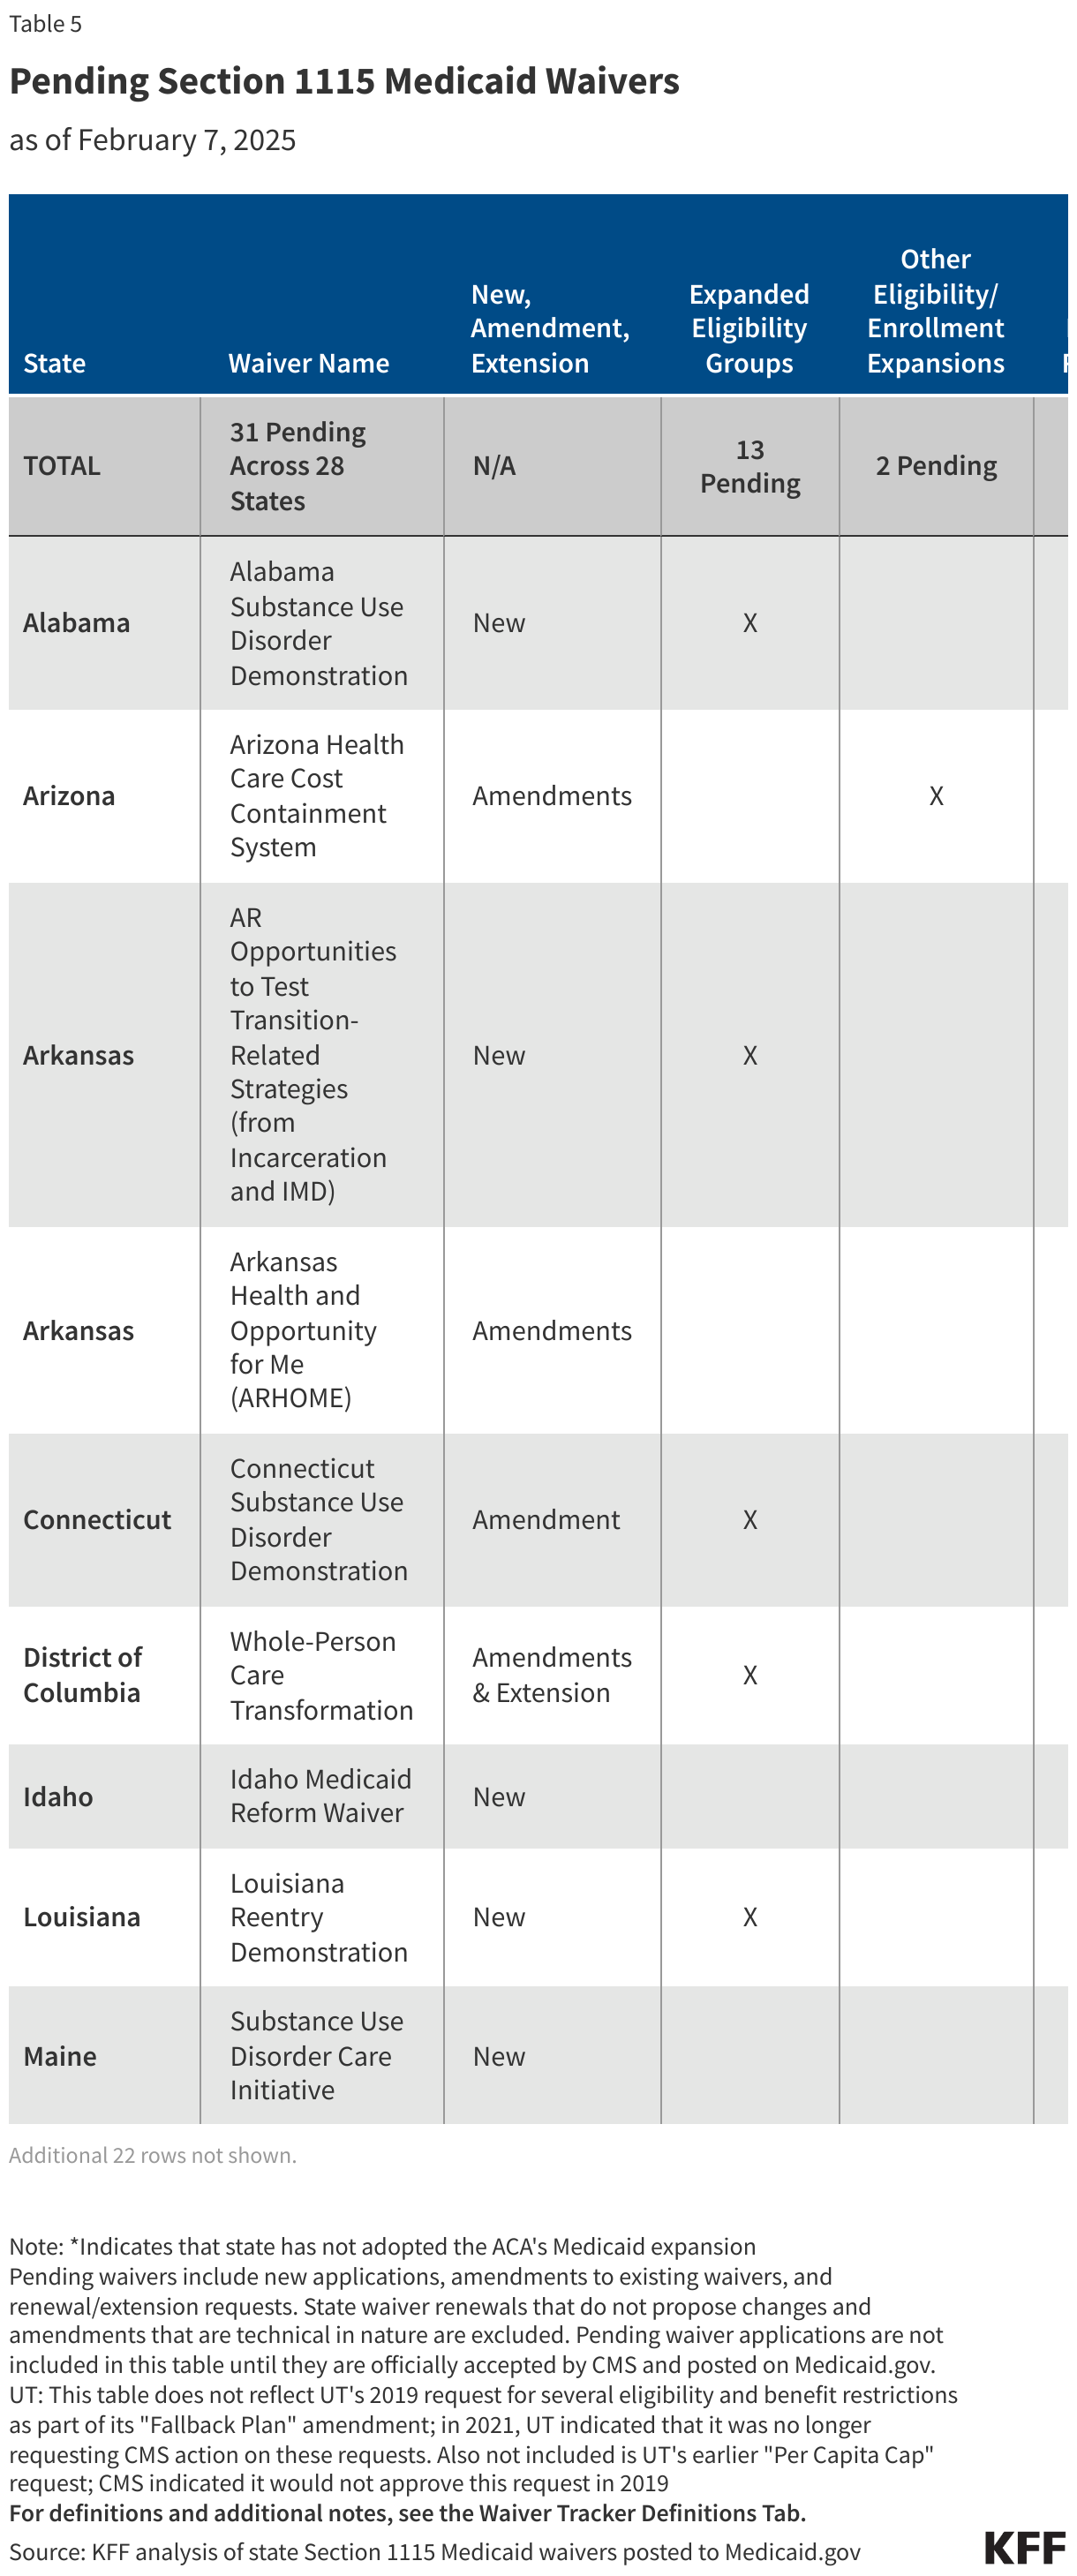
The official guidance coming out of CMS reflects a clear ideological shift regarding the purpose of the Medicaid safety net.
n
In the March 2025 letter rescinding HRSN guidance, CMS officials argued that Medicaid resources should be prioritized for direct medical services rather than "ancillary" social supports like housing or air conditioning. The administration’s stance is that while social factors are important, they fall outside the primary statutory mission of Medicaid.
n
Conversely, state health officials in Democratic-led states have expressed concern. In response to the July 2025 guidance ending continuous eligibility, several state Medicaid directors argued that the move would lead to increased "churn" and higher long-term costs as patients lose access to preventive care and end up in emergency rooms.
n
Regarding the phasing out of DSHP funding, the administration stated that the move is necessary to ensure "fiscal accountability." By limiting the ability of states to use DSHP to "finance their share of Medicaid," the federal government aims to reduce the overall federal expenditure on the program. Critics, however, argue this will leave massive holes in state budgets that currently support public health clinics and mental health services.
Implications: The Future of the Medicaid Safety Net
The implications of these shifts are profound and multifaceted, affecting millions of enrollees and the financial stability of state healthcare systems.
1. Increased Administrative Burden and "Churn"
The return of work requirements and the end of continuous eligibility will necessitate a massive administrative build-out. States will need to develop systems to track work hours, verify exemptions, and process more frequent eligibility redeterminations. Historically, work requirements have led to coverage losses not just for those who don’t work, but for those who fail to navigate the complex paperwork required to prove they are working.
2. The Narrowing of "Whole-Person" Care
The rescission of HRSN guidance marks a retreat from the "whole-person" care model. States that were beginning to use Medicaid funds to stabilize housing for the homeless or provide medically tailored meals for diabetics will now have to find alternative funding or shutter these programs. This could lead to a resurgence in the "siloed" approach to healthcare, where medical treatment is divorced from the social conditions that drive illness.

3. Fiscal Pressure on States
The phase-out of DSHP funding and workforce strengthening initiatives will force states to make difficult choices. Without federal matching funds for these programs, states may be forced to cut provider reimbursement rates or limit optional benefits (such as dental or vision care) to balance their budgets.
4. A New Frontier for Justice-Involved Care
One of the few areas with bipartisan interest is the "pre-release" coverage for incarcerated individuals. By allowing Medicaid to cover services 30 to 90 days before an individual is released from prison, states hope to reduce recidivism and overdose deaths. While the Trump administration has approved several of these waivers, the promised "updated guidance" in 2027 will likely introduce stricter limits on the types of services covered, potentially focusing more on substance use disorder (SUD) than general primary care.
In conclusion, the Section 1115 waiver landscape has moved from an era of expansion and social integration to one of restriction and work-focused eligibility. As states move toward the 2027 federal deadline, the true impact of these policies on the health and economic stability of the nation’s most vulnerable populations remains to be seen. What is certain is that the "flexibility" of Section 1115 is being used as a powerful lever to redefine the very nature of the American social contract.

