
WASHINGTON D.C. — The landscape of American healthcare is undergoing its most significant transformation since the passage of the Affordable Care Act (ACA), driven by a fundamental redirection of Section 1115 Medicaid demonstration waivers. Once a primary tool for the Biden administration to expand social safety nets and address health inequities, these waivers are now being recalibrated under the second Trump administration to emphasize fiscal restraint, personal responsibility, and the implementation of mandatory work requirements.
n
According to the latest analysis of state Section 1115 Medicaid waivers, the Department of Health and Human Services (HHS) is overseeing a complex transition. As of late 2025, the focus has shifted from "Health-Related Social Needs" (HRSN) toward a "work-first" philosophy, catalyzed by the 2025 tax and spending law. This shift represents a departure from federal policies that prioritized continuous coverage and social determinants of health, moving instead toward a model that conditions eligibility on employment and limits the duration of retroactive coverage.
n
Main Facts: The Changing Face of Medicaid Demonstration
n
Section 1115 waivers grant the HHS Secretary the authority to allow states to bypass federal Medicaid statutes to test "experimental, pilot, or demonstration" projects that promote the program’s objectives. While nearly every state operates at least one such waiver, the definition of what "promotes the objectives" of Medicaid has become a political and legal battleground.
n
Key findings from the current tracker include:
n
- n
- Mandatory Work Requirements: Under the 2025 reconciliation law, all states must condition Medicaid eligibility for ACA expansion adults on meeting work requirements by January 1, 2027.
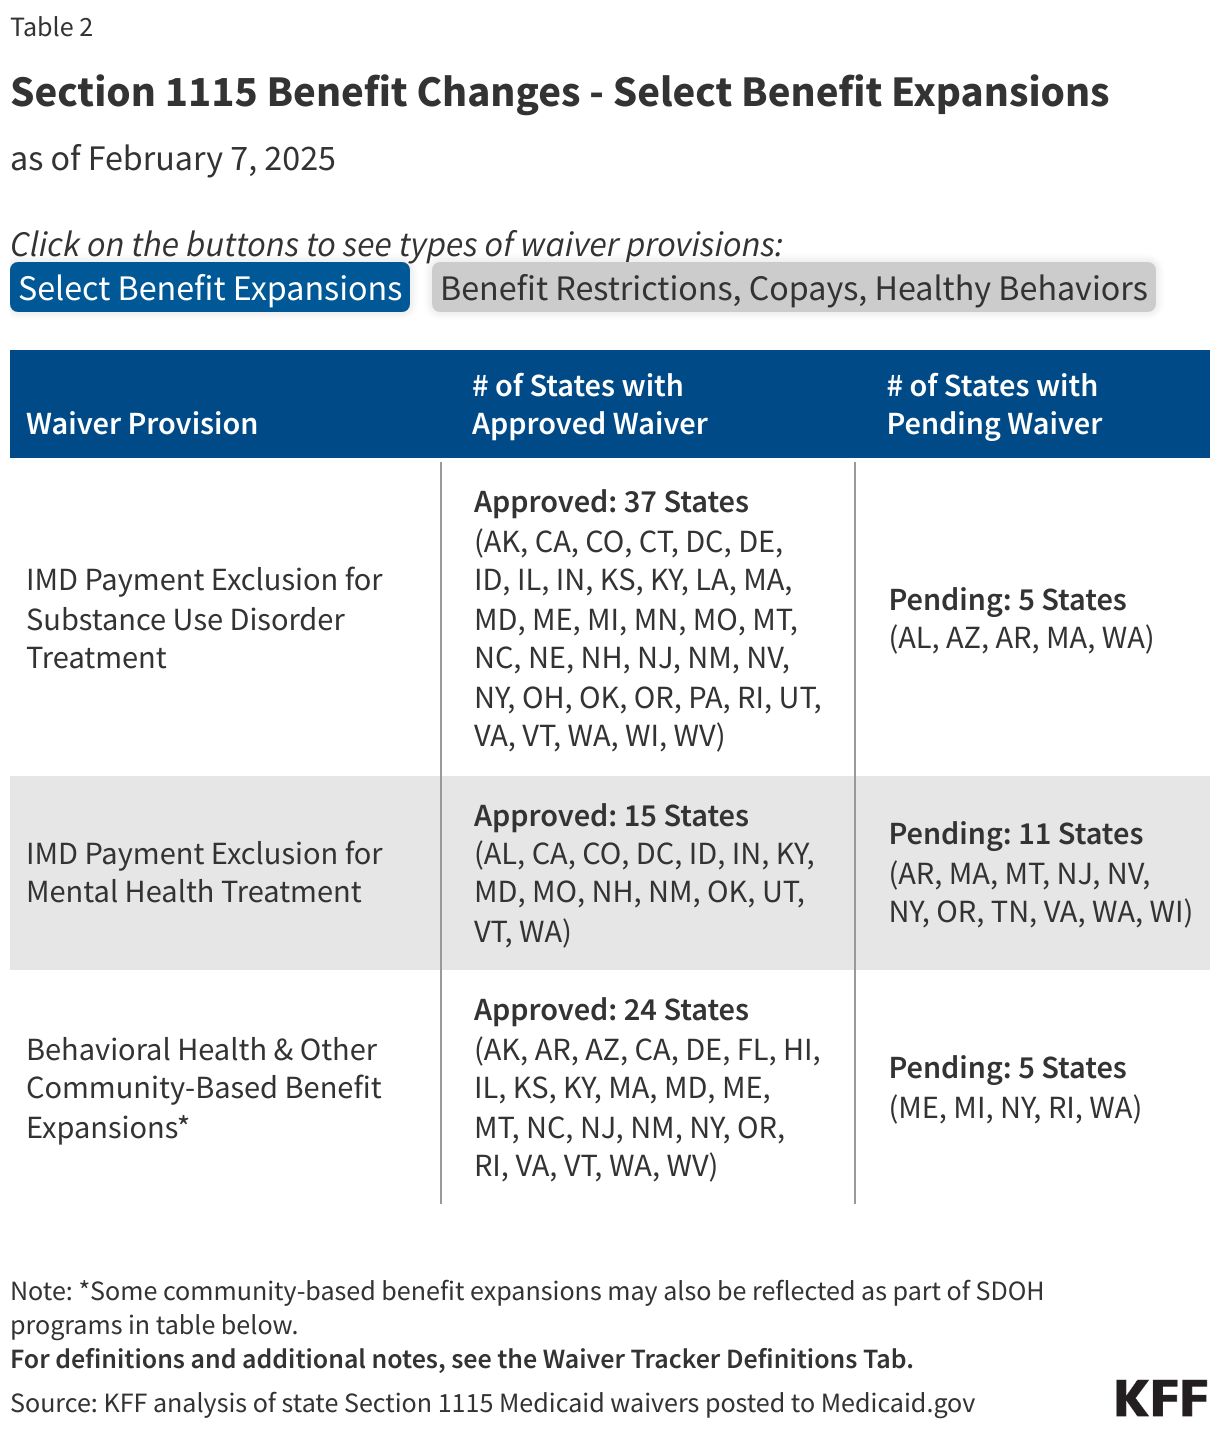
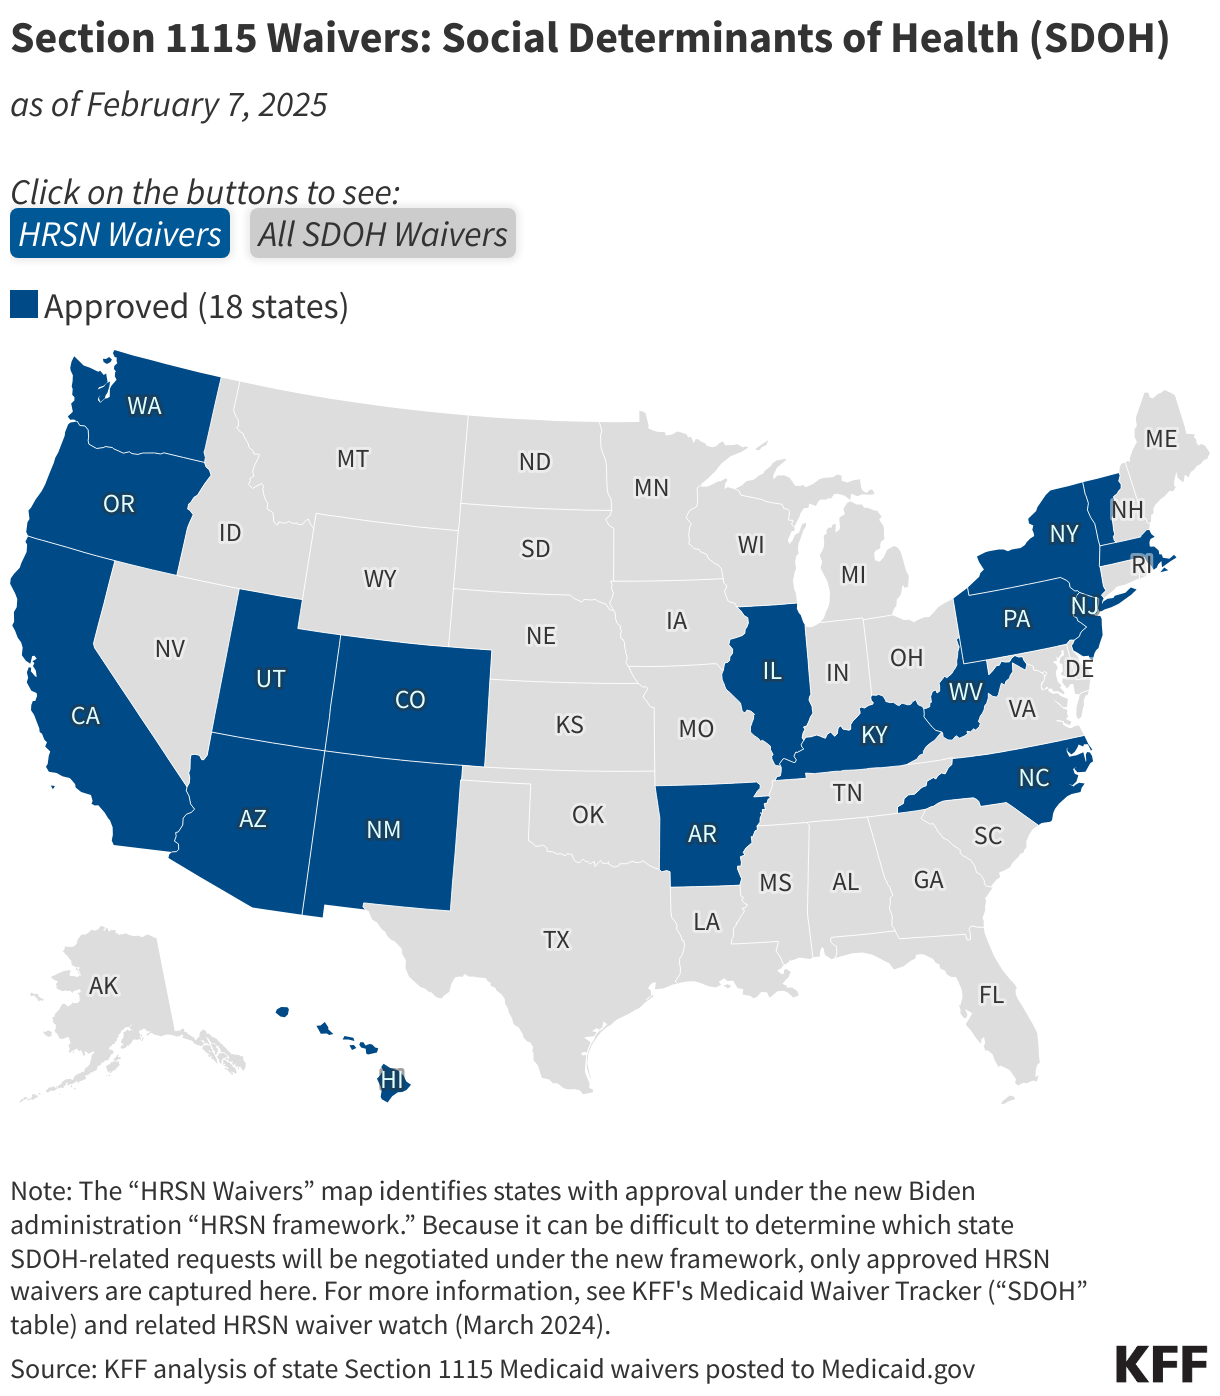
- The Rescission of HRSN Guidance: In March 2025, the Trump administration rescinded the Biden-era framework for Health-Related Social Needs, which had allowed states to use Medicaid funds for housing and nutrition supports.
- The End of Multi-Year Eligibility: New guidance issued in July 2025 effectively ended the approval of multi-year continuous eligibility waivers for children, a policy previously touted as a cure for "enrollment churn."
- Phasing Out Infrastructure Funding: Federal funding for "Designated State Health Programs" (DSHP) is being phased out, forcing states to find alternative revenue streams for delivery system reforms.
n
n
n
n
n
Chronology: From Social Safety Net to Workforce Activation (2022–2027)
n
The evolution of Section 1115 policy over the last five years reveals a stark ideological divide between administrations, creating a volatile environment for state health administrators.
n
2022–2023: The Expansion of Social Determinants
n
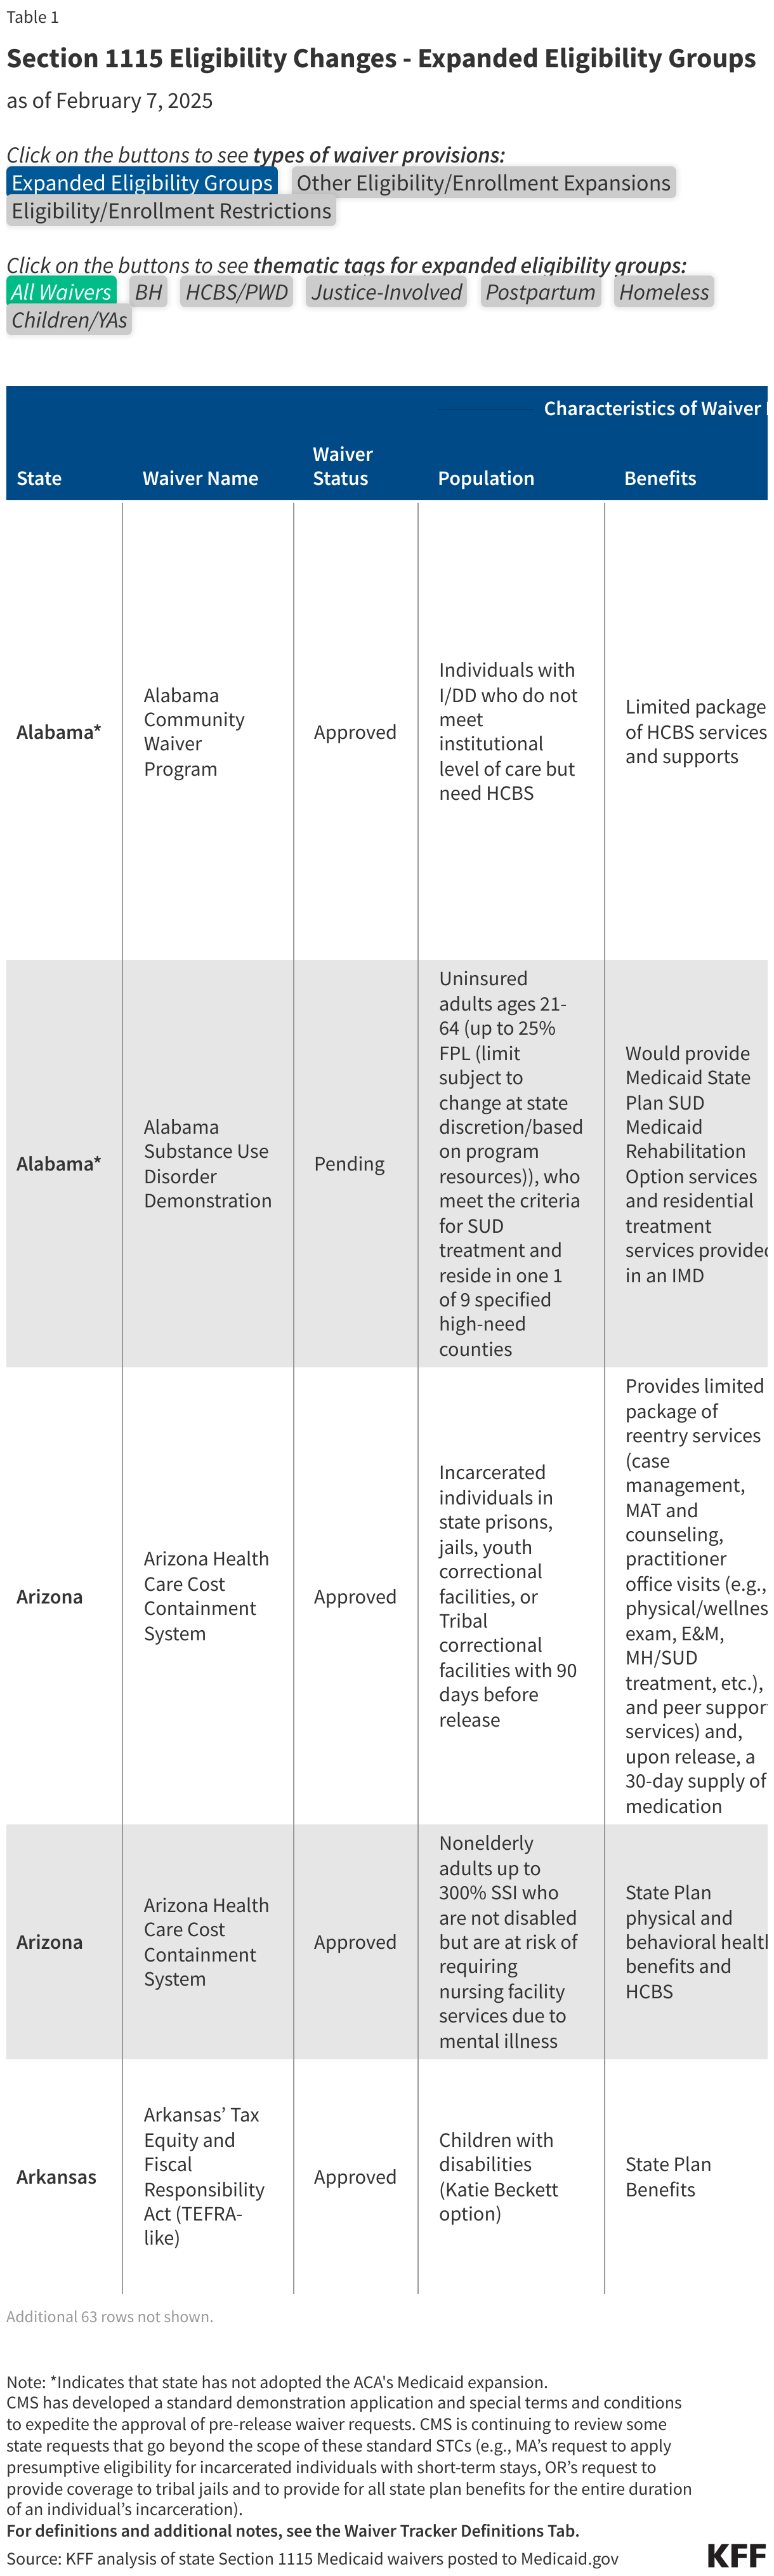
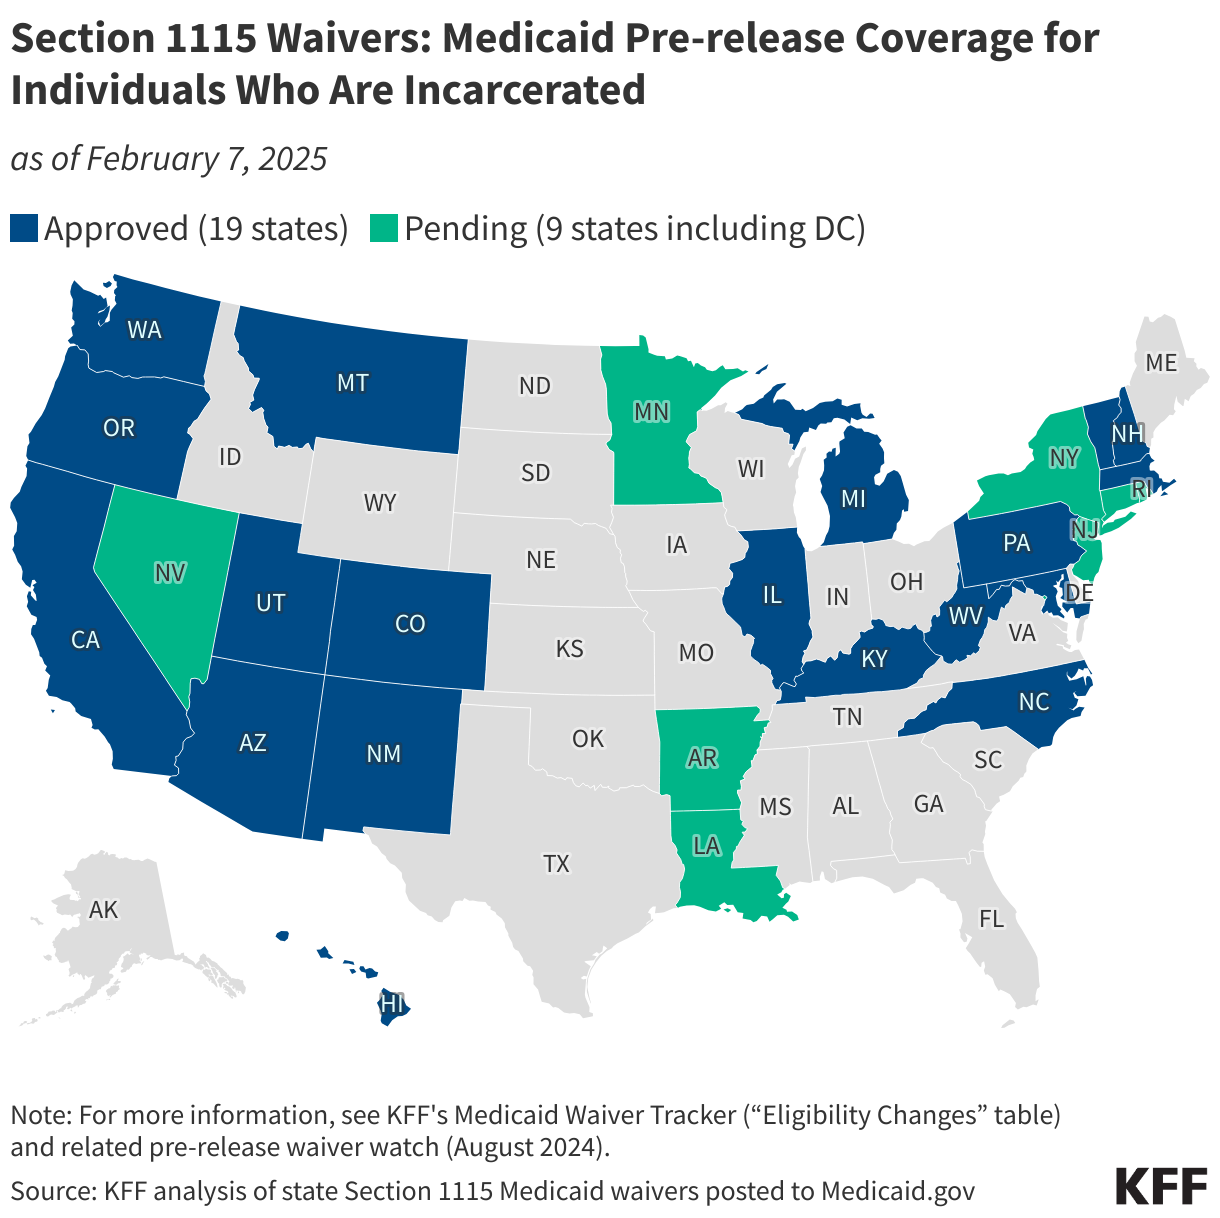
Under the Biden administration, CMS encouraged states to address the "whole person." In 2022, CMS announced a landmark opportunity to address HRSN, followed by a detailed framework in 2023. This led to the approval of waivers in states like Oregon and Massachusetts that covered housing transitions and medically tailored meals. Simultaneously, CMS released guidance in April 2023 allowing states to provide pre-release services to incarcerated individuals—a partial waiver of the decades-old "inmate exclusion policy."
n
2024: Legal Challenges and Legislative Shifts
n
The tide began to turn as legal challenges reached the courts. In June 2024, the U.S. District Court for the District of Columbia vacated federal approval for Indiana’s "Healthy Indiana Plan 2.0," striking down the state’s authority to charge premiums and waive retroactive eligibility. However, the passage of the 2025 tax and spending law later that year provided a legislative mandate for policies that the courts had previously questioned.
n
2025: The Trump Administration’s "Case-by-Case" Reversal
n
Upon taking office, the second Trump administration moved quickly to dismantle the HRSN framework. In March 2025, CMS rescinded the Biden-era guidance, moving to a "case-by-case" review process that significantly narrowed the scope of approved social supports. By July 2025, new guidance was issued to halt multi-year continuous eligibility for children, and workforce initiatives for primary care and behavioral health were slated for phase-out.
n
2026–2027: The Implementation Deadline
n
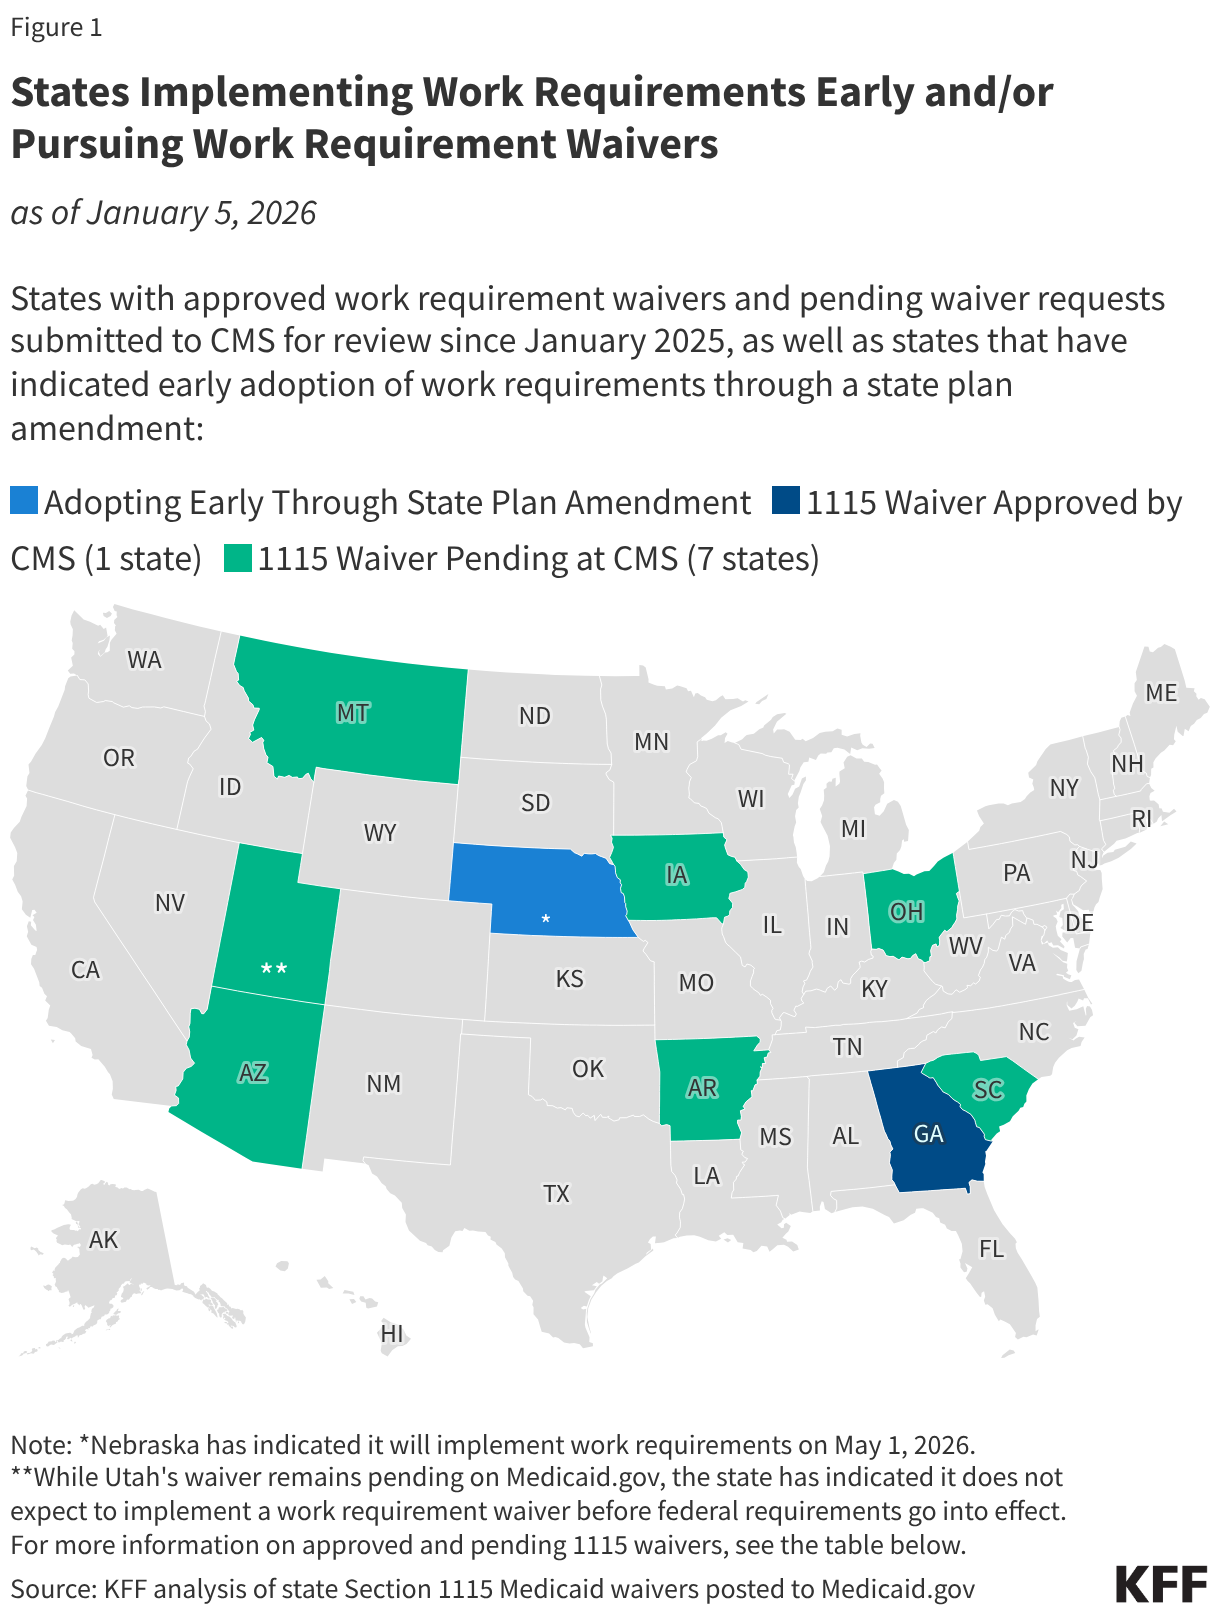
The current period is defined by "early adoption." States like Nebraska, Montana, and Iowa have announced plans to implement work requirements ahead of the January 2027 federal deadline. By September 30, 2026, the tracker indicates a landscape dominated by these transitions, with states scrambling to update their State Plan Amendments (SPAs).
n
Supporting Data: The Landscape of Waivers
n
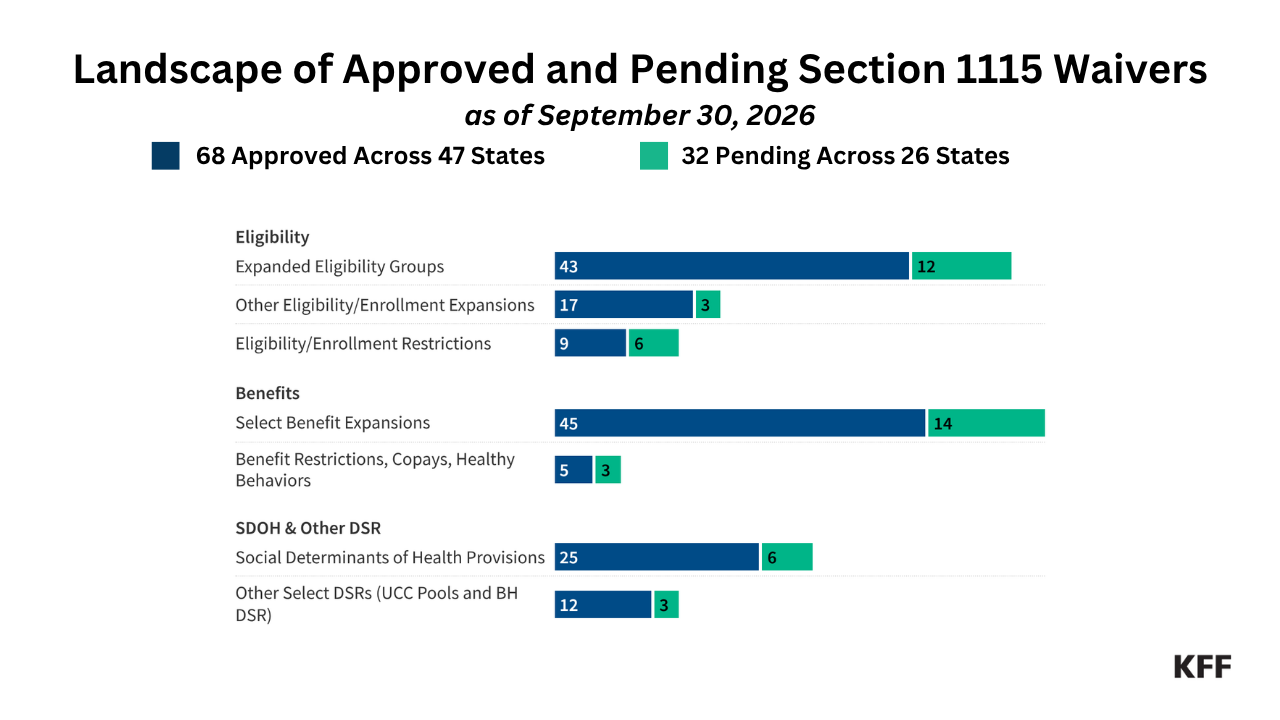
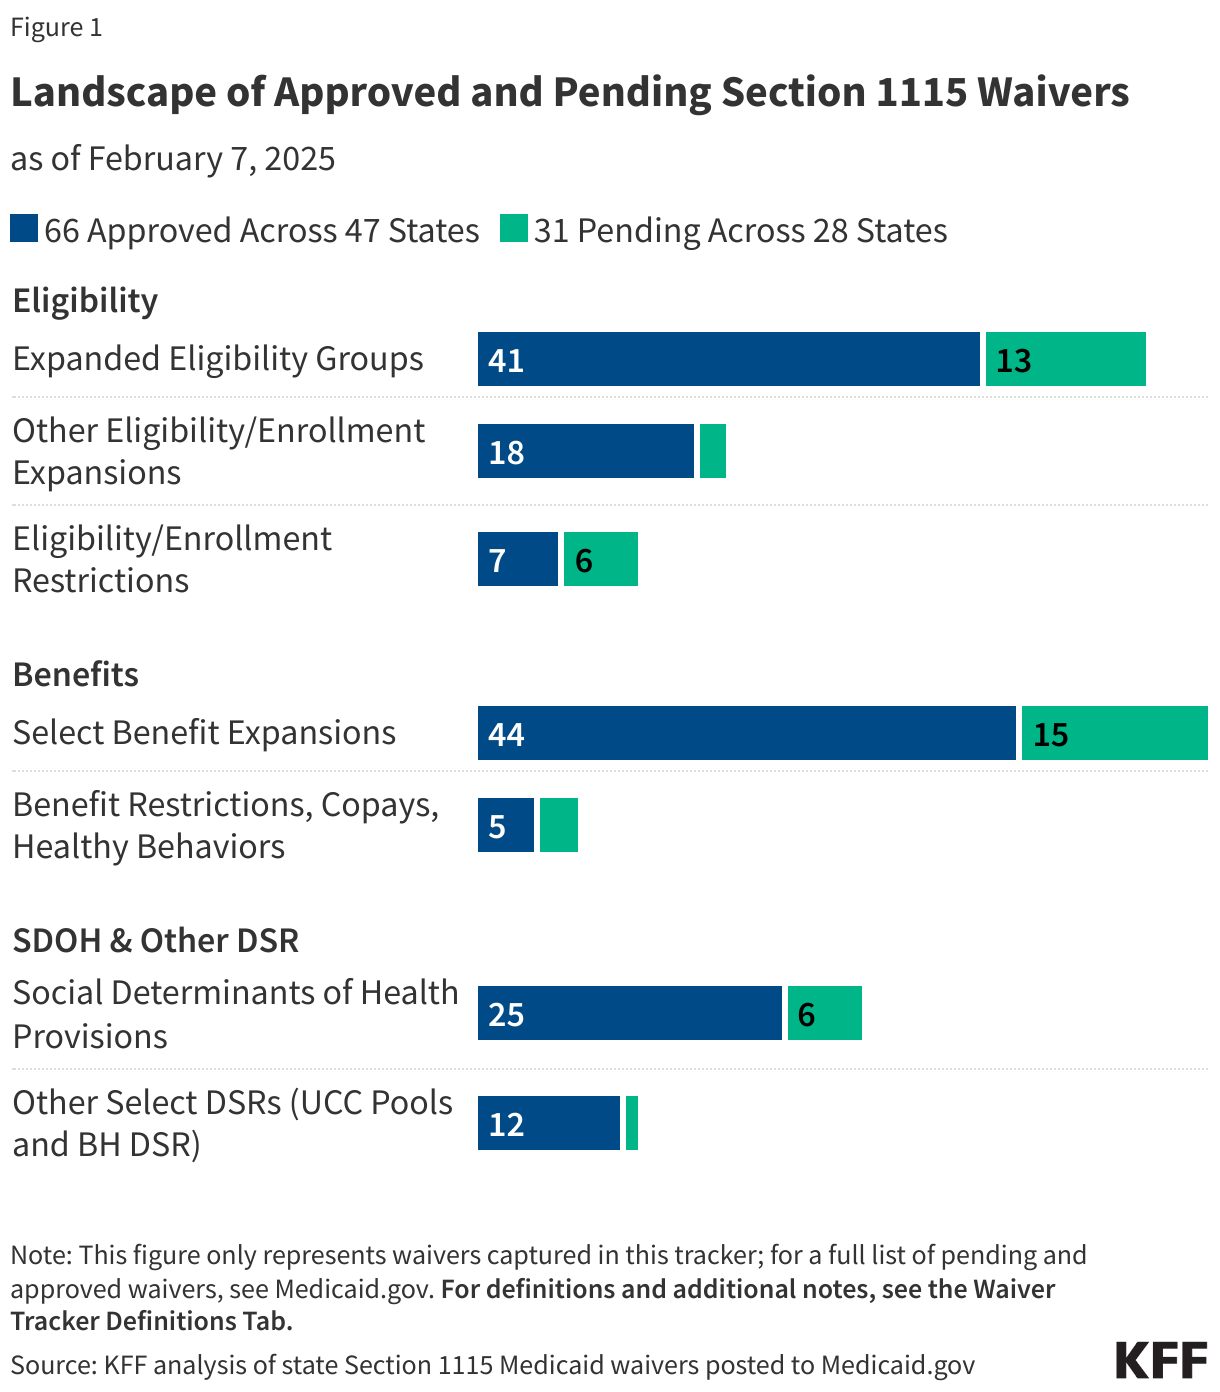
The current data reveals a high volume of pending and approved waivers that reflect this new reality.

n
Eligibility Restrictions and Work Requirements
n
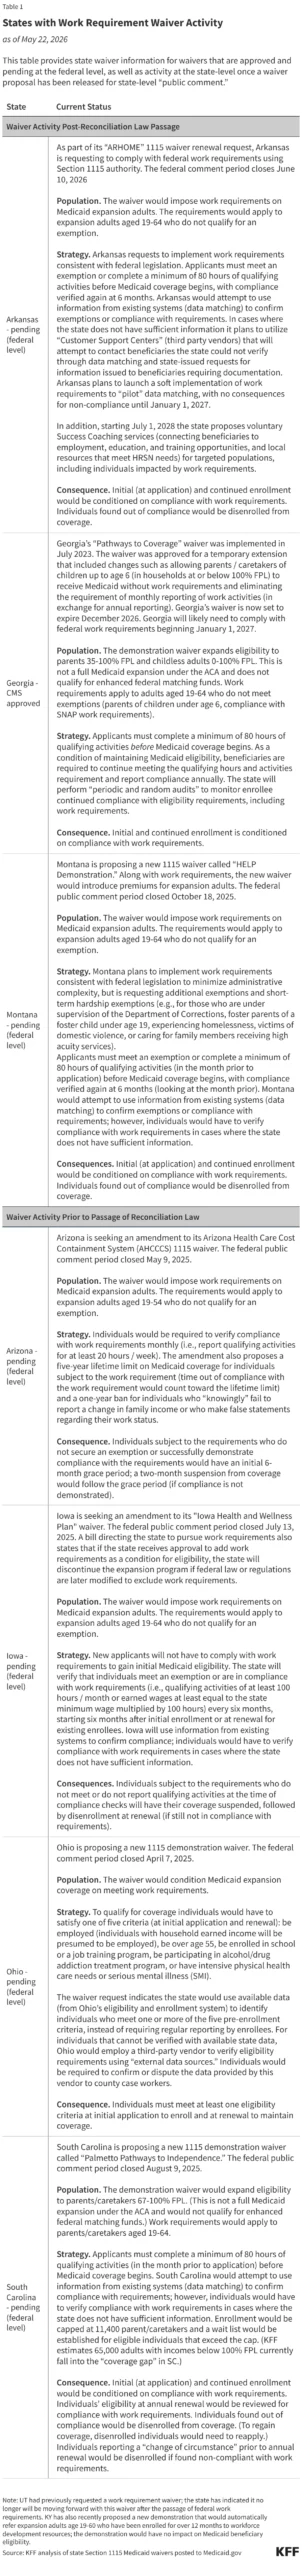
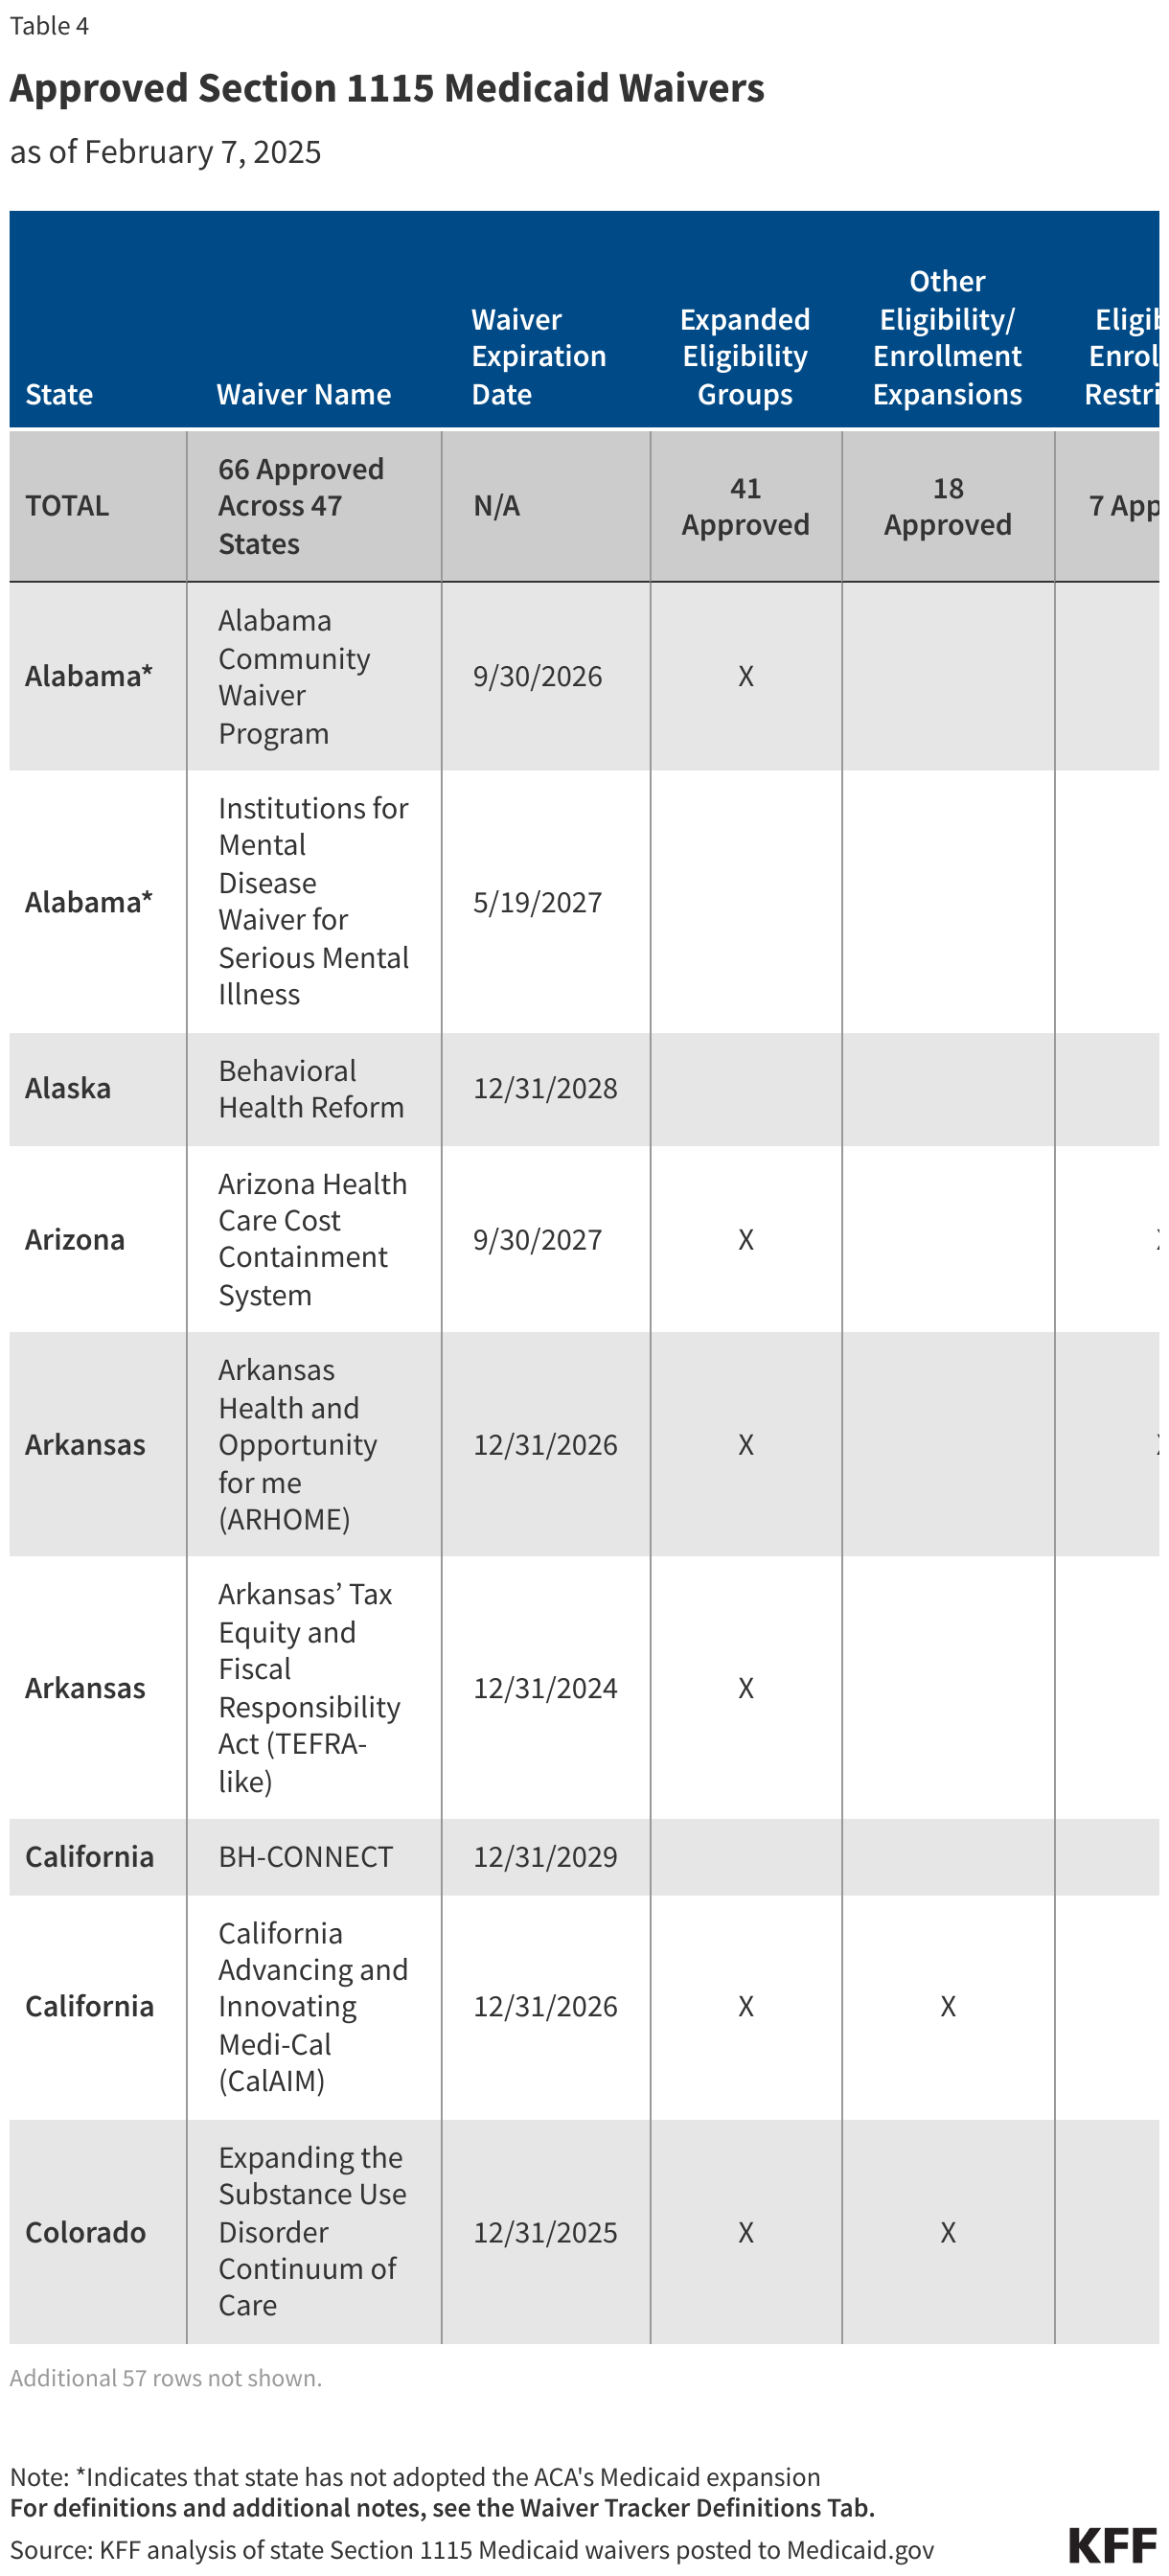
While Georgia remains the only state with an active work requirement waiver as of late 2025 (following the expiration of its litigation-protected status), the focus has shifted to SPAs.
n
- n
- Nebraska: Set to begin enforcement on May 1, 2026.
- Montana: Set for July 1, 2026.
- Iowa: Set for December 1, 2026.
- Arkansas: Planning a "soft launch" in July 2026, though disenrollments will not begin until the federal mandate in 2027.
n
n
n
Retroactive Eligibility and Premiums
The 2025 law introduces significant restrictions on retroactive coverage. Starting January 1, 2027, retroactive coverage will be limited to one month for ACA expansion enrollees and two months for traditional enrollees, down from the standard three-month policy. Furthermore, while the Biden administration phased out premiums in states like Arkansas and Montana, the new administration is reconsidering these "skin in the game" policies, though the 2025 law will eventually prohibit premiums for ACA expansion adults by 2028.
Social Determinants of Health (SDOH)
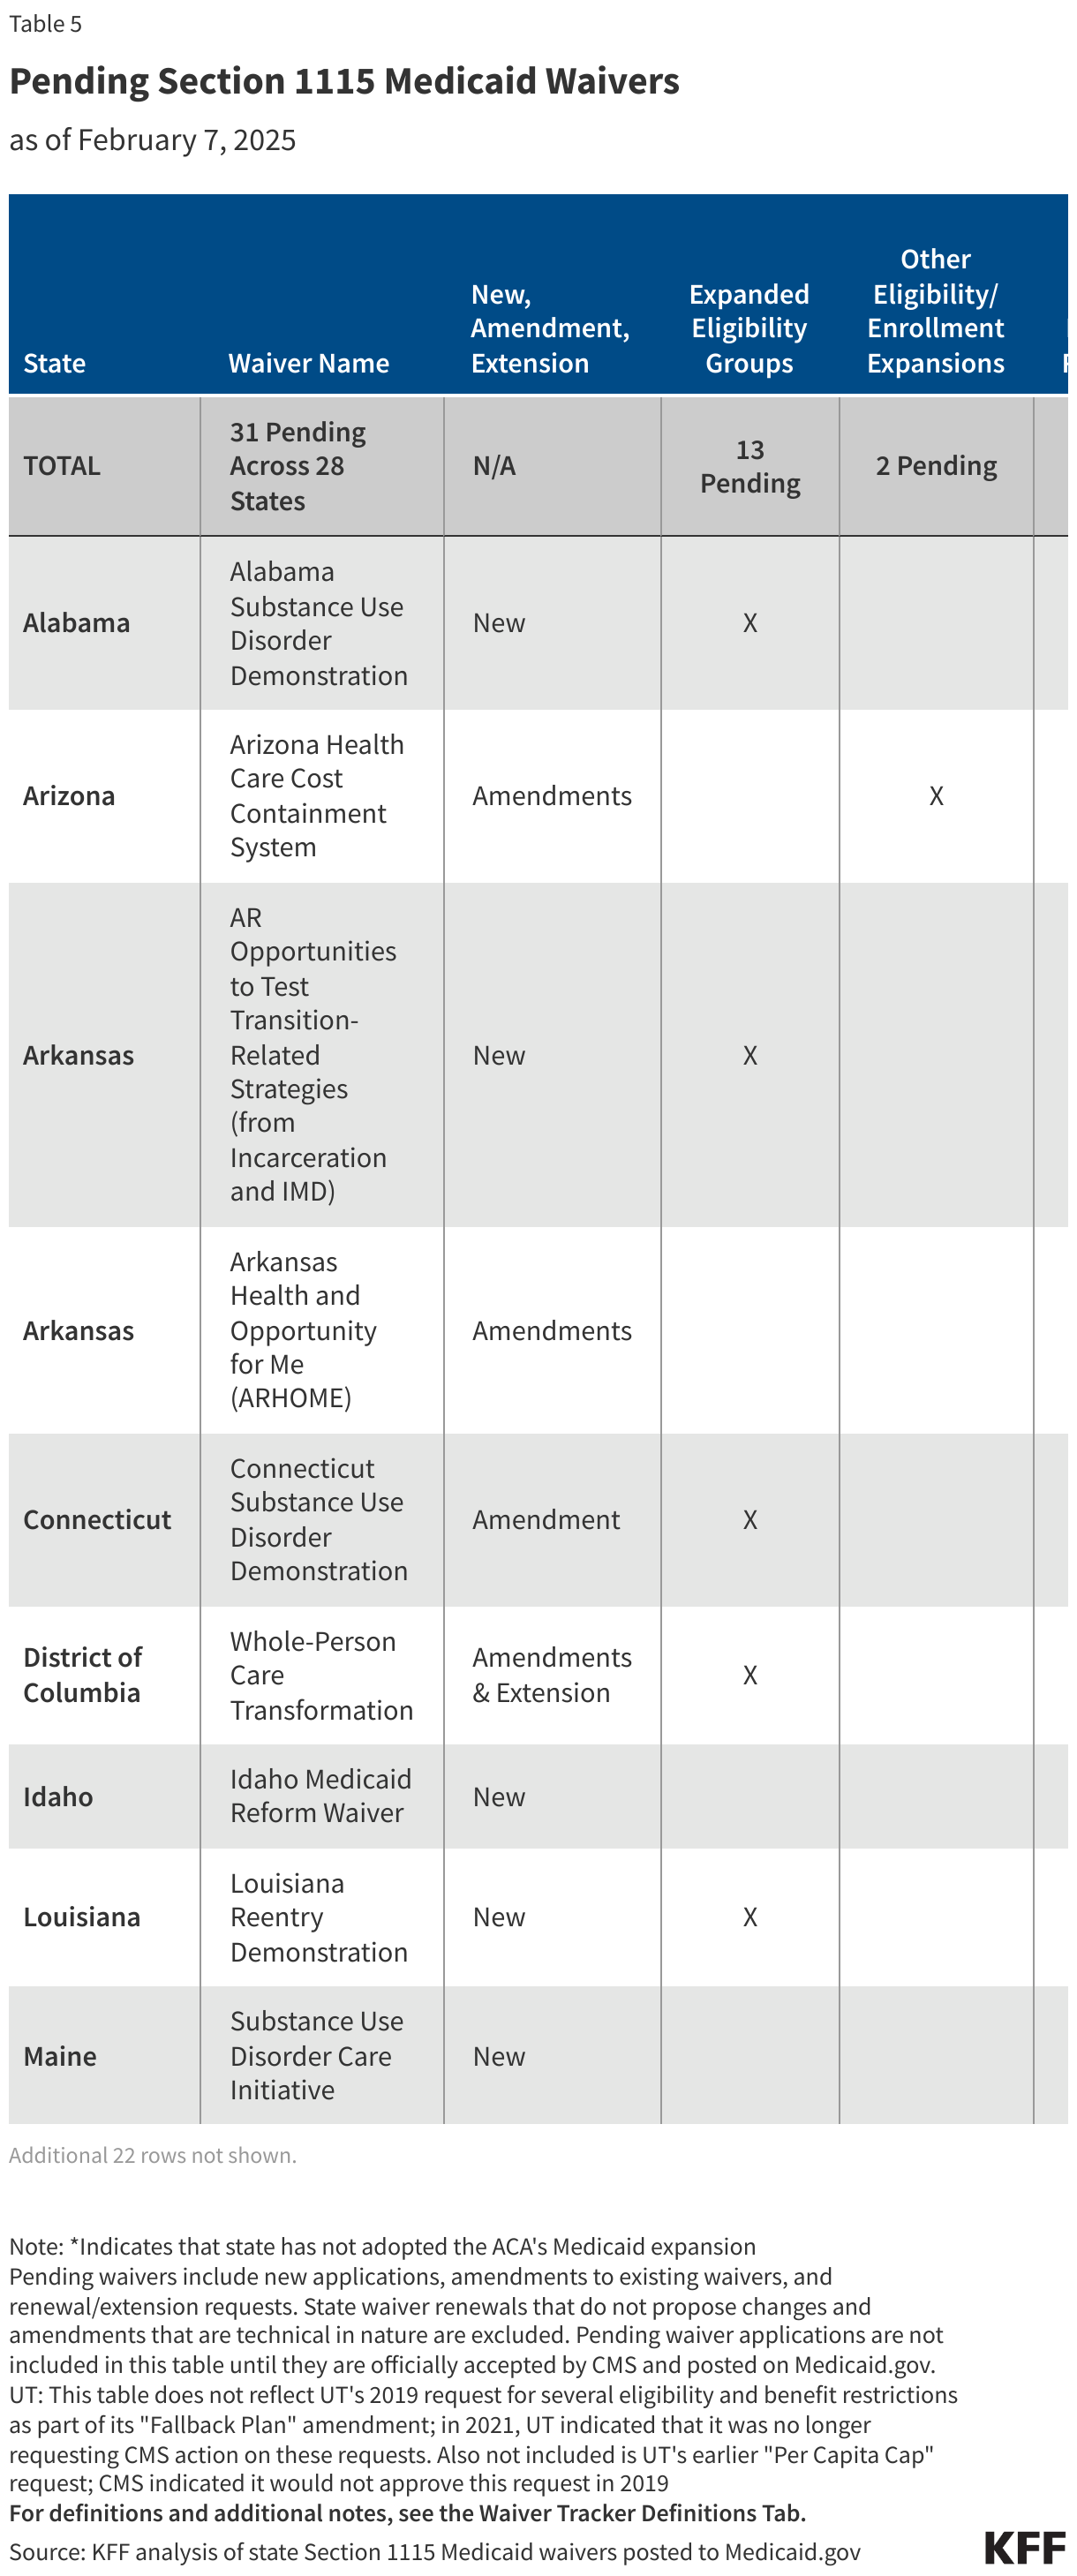
Despite the rescission of the HRSN framework, 19 states currently have some form of approved SDOH provision. However, the tracker shows a growing list of "pending" provisions as CMS transitions to its more restrictive case-by-case review. Most states with approved HRSN services (marked with a "+" in the tracker) had those approvals granted under the previous administration; their future during the renewal process remains uncertain.
Official Responses: States and Federal CMS
The response to these changes has been polarized along partisan lines, reflecting the broader national debate over the purpose of Medicaid.
The Centers for Medicare & Medicaid Services (CMS):
In its March 2025 bulletin, CMS stated that while it would not "negate existing approvals" for social needs, the previous framework was overly broad. "CMS will now consider state applications for services and supports on a case-by-case basis, ensuring that Medicaid remains focused on its core mission of providing medical assistance," the agency noted in its rescission of the HRSN guidance.
State-Level Proponents:
Governors in states like Nebraska have embraced the shift. "Implementing work requirements early allows us to promote the dignity of work and ensure our Medicaid program is sustainable for those who truly need it," a spokesperson for the Nebraska Department of Health and Human Services stated.
Legal and Advocacy Groups:
Advocacy groups have expressed alarm, particularly regarding the end of continuous eligibility for children. The Georgetown University Center for Children and Families warned that ending multi-year eligibility will lead to increased "churn," where eligible children lose coverage due to administrative hurdles. "We are moving backward on child health outcomes to satisfy a fiscal ideology," the Center noted in a recent brief.
Implications: The Long-term Impact on Access and Equity
The pivot in Section 1115 waiver policy has profound implications for the 80 million Americans enrolled in Medicaid.

1. Increased Administrative Churn
The combination of work requirements and the end of continuous eligibility is expected to increase "churn." Data shows that when administrative requirements increase, even eligible individuals lose coverage because of the difficulty of reporting hours or navigating complex state portals. This often leads to delayed care and higher costs when enrollees eventually return to the system in emergency rooms.
2. The Narrowing of "Medical Assistance"
By rescinding the HRSN framework, the federal government is narrowing the definition of healthcare. For states like Oregon, which used waivers to provide air conditioners to enrollees with asthma during heatwaves or housing support for the homeless, the "case-by-case" approach creates budget uncertainty. If these services are no longer reimbursable via Medicaid, states must either cut the programs or fund them entirely through state tax dollars.
3. Justice-Involved Reentry Risks
While the Trump administration approved four reentry waivers in September 2026, the promise of "updated guidance" within a year suggests a potential tightening of who qualifies for pre-release services. This creates a precarious situation for the 19 states that had built robust community reentry programs under the Biden-era guidance, potentially impacting recidivism and overdose rates among the formerly incarcerated.
4. Fiscal Pressure on States
The phase-out of Designated State Health Programs (DSHP) funding removes a flexible pot of money that states used to innovate. Without this federal match, many delivery system reforms—such as integrated behavioral health clinics or workforce incentive programs—may be scaled back or eliminated.
Conclusion
The Section 1115 waiver landscape has moved from an era of "innovation through expansion" to an era of "flexibility through restriction." As 2027 approaches, the focus of the Medicaid program is being redefined. Whether this shift succeeds in increasing workforce participation without causing a spike in the uninsured rate remains the most critical question facing health policy experts today. For now, states find themselves in a race to comply with a new federal mandate that prioritizes the "work-first" model, fundamentally altering the social contract of the nation’s largest health insurer.

