
WASHINGTON D.C. — In a fundamental restructuring of international development policy, the United States government has entered a new era of "conditional partnership" with its global health allies. One year after the unveiling of the America First Global Health Strategy on September 18, 2025, the landscape of international aid has been transformed from a model of long-term assistance to one of mandatory fiscal transition.
n
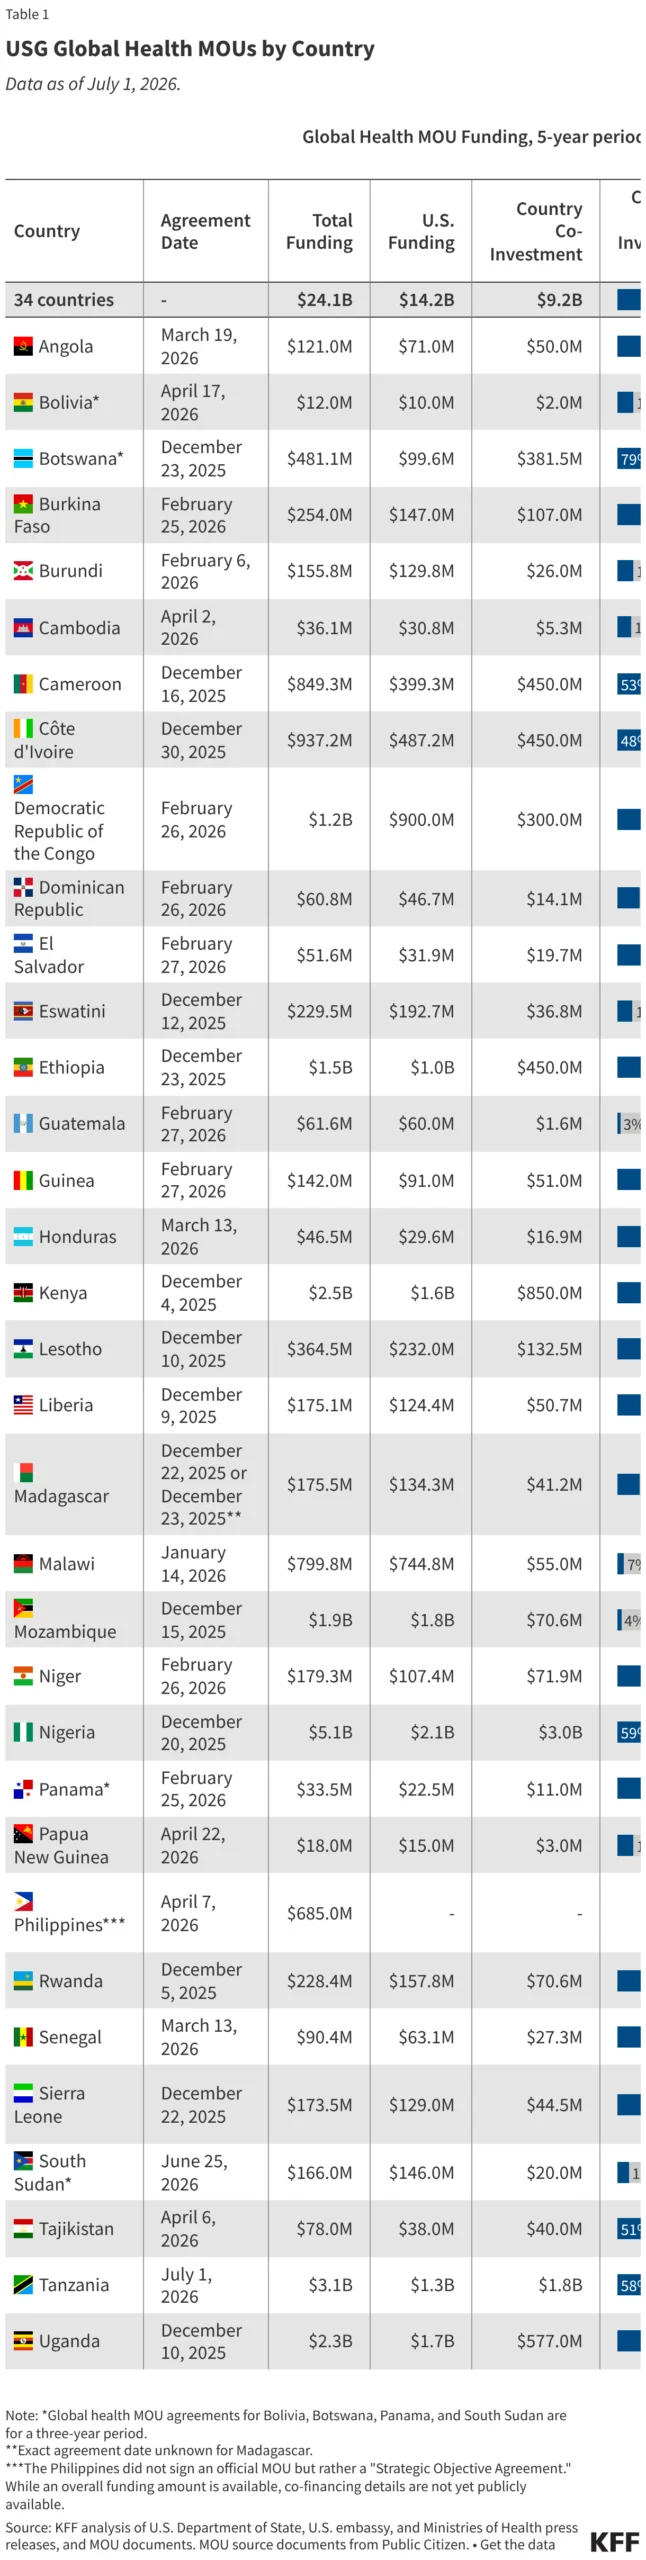
As of September 11, 2026, the U.S. Department of State and the U.S. Agency for International Development (USAID) have successfully negotiated bilateral health cooperation agreements with 34 nations. These agreements, formalized through Memorandums of Understanding (MOUs), outline a rigorous five-year glide path (2026–2030) designed to reduce U.S. financial outlays while compelling partner nations to assume the majority of their own public health costs.
n
The strategy marks the most significant pivot in U.S. global health policy since the inception of PEPFAR in 2003, signaling a move away from "open-ended" funding toward a "resilient and durable" model of self-reliance. However, with a projected $7.3 billion reduction in U.S. funding across the participating countries, the stakes for global health security have never been higher.
n
n
Main Facts: A New Architecture for Global Health
n
The America First Global Health Strategy is predicated on the "Country Ownership" model. Unlike previous iterations of health diplomacy that focused primarily on disease-specific outcomes (such as HIV/AIDS, Malaria, or Tuberculosis), the current strategy prioritizes the "graduation" of partner nations from U.S. financial dependence.

n
Key Pillars of the Strategy:
n
- n
- Bilateral MOUs: Five-year strategic plans (2026–2030) that serve as a roadmap for U.S. disengagement.
- Mandatory Co-Investment: Partner countries must pledge to increase domestic health spending—often referred to as "co-financing"—in direct proportion to the decrease in U.S. assistance.
- Systemic Resiliency: Shifting focus from providing services to building the infrastructure (supply chains, workforce training, and data systems) that allows countries to manage their own health threats.
- Strategic Objective Agreements: In cases like the Philippines, where a formal MOU was not utilized, "Strategic Objective Agreements" serve a similar purpose, albeit with different legal frameworks.
n
n
n
n
n
To date, 34 countries have signed on to this framework. While the majority of these agreements cover a five-year window, exceptions exist for countries facing unique political or economic instability, such as Bolivia, Botswana, Panama, and South Sudan, which have entered into shorter, three-year agreements.
n
n
Chronology: From Concept to Implementation
n
The rollout of this strategy has been rapid, characterized by high-level diplomatic pressure and a clear mandate from the executive branch to reform the foreign aid budget.
n
- n
- September 18, 2025: The U.S. Government officially releases the America First Global Health Strategy report. The document outlines a vision where U.S. taxpayers are no longer the primary financiers of global health in middle-income and developing nations.
- Late 2025: The first wave of MOUs is signed. Early adopters include nations with long-standing bilateral ties that were already trending toward middle-income status.
- January 13, 2026: The first comprehensive tracker of these agreements is published, providing the public with data on funding levels and co-financing requirements.
- July 1, 2026: Data reveals that 34 countries have formalized their transition plans. The Philippines signs a "Strategic Objective Agreement," a notable variation in the standard MOU format.
- September 11, 2026: The State Department issues an update reflecting the most recent signatories and the total projected funding cuts, which have now reached a staggering 34% reduction compared to the previous five-year period.
- Late 2026 (Projected): Full-scale implementation begins, with the first "step-down" in U.S. funding scheduled for the 2027 fiscal year.
n
n
n
n
n
n
n
n
Supporting Data: The $7.3 Billion Gap
n
The most striking feature of the America First Global Health Strategy is its fiscal impact. According to a KFF analysis of State Department and Ministry of Health documents, the 34 countries currently under MOUs will see a collective $7.3 billion reduction in U.S. global health funding over the next five years.
n
The Funding Cliff
n
Historically, the Global Health Programs (GHP) account provided consistent, often increasing, support. For the period of 2021–2025, funding for these 34 countries was robust. Under the new 2026–2030 MOUs, however, that funding is set to drop by an average of 34%.

- Top-Line Reduction: -$7.3 billion.
- Average Percentage Change: -34% per country.
- Exceptions: Botswana and South Sudan, due to their specific health crises and shorter agreement windows, have slightly different funding trajectories, though the long-term goal of U.S. reduction remains constant.
Co-Financing and Share
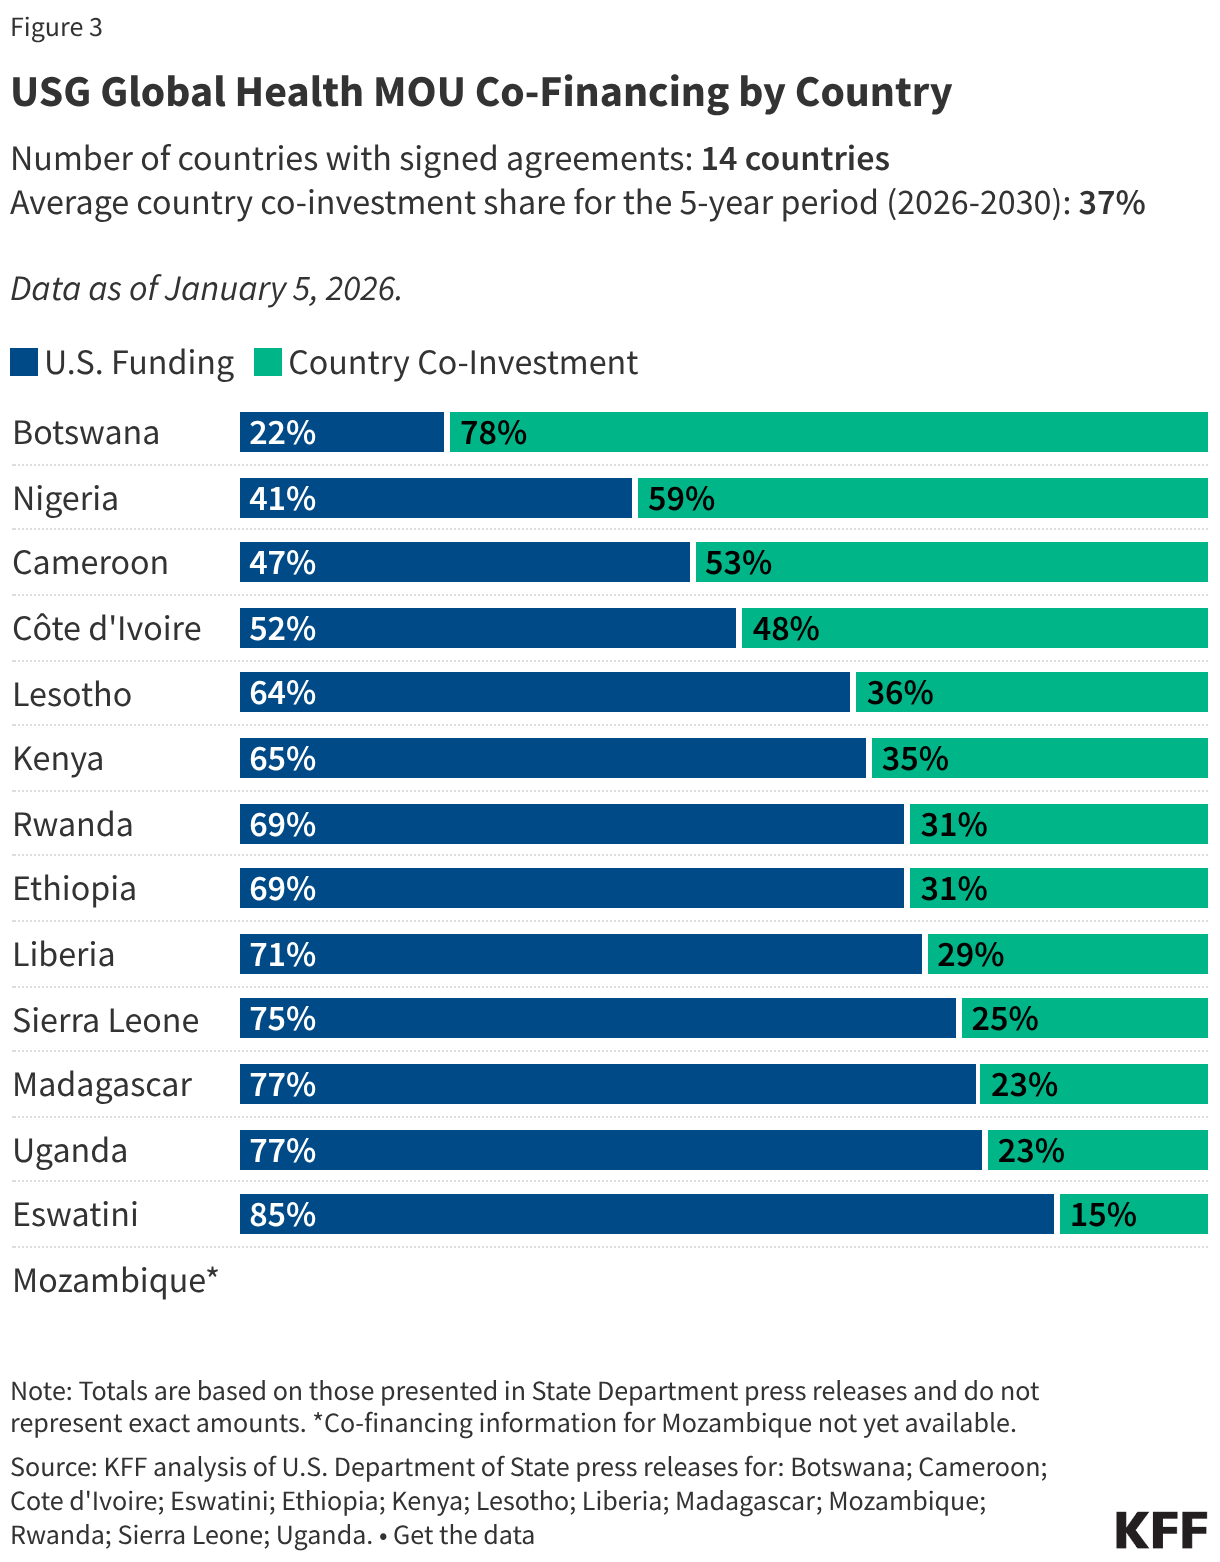
The "America First" model relies on a "Stacked Bar" financial structure. As the blue bar (U.S. funding) shrinks annually, the green bar (Partner Country Co-Investment) must grow. For many Sub-Saharan African nations, this requires increasing domestic health budgets by 5% to 10% annually—a difficult feat for economies struggling with inflation and debt.
Programmatic Focus
The MOUs are not "blank checks." They are targeted at specific program areas:
- Global Health Security (GHS): Nearly every MOU includes a mandate for GHS, focusing on outbreak preparedness and response to ensure that local health threats do not become global pandemics.
- HIV/AIDS and Malaria: Continued but diminishing support, with an emphasis on transferring the "last mile" delivery of drugs to local health ministries.
- Maternal and Child Health: A core component of the "resilient systems" goal.
Official Responses: Conflicting Visions of Sustainability
The implementation of these MOUs has sparked a polarized debate within the international community.
The U.S. Administration’s Stance
The State Department has defended the strategy as a necessary evolution of the "donor-recipient" relationship. In a recent briefing, officials stated:

"For too long, U.S. assistance has been a permanent fixture rather than a temporary bridge. The America First Global Health Strategy honors the American taxpayer while empowering our partners to take the lead in their own destiny. True sovereignty begins with the ability to care for one’s own citizens."
Partner Country Reactions
The response from partner countries has been a mix of pragmatic acceptance and quiet concern.
- The Philippines: By opting for a "Strategic Objective Agreement" rather than a standard MOU, Manila has signaled a desire for more flexibility, though they remain committed to the overall funding goals.
- African Union Representatives: Several health ministers from Southern Africa have expressed concern that the "funding cliff" is too steep. "We embrace ownership," one minister noted anonymously, "but you cannot build a resilient system while simultaneously removing the scaffolding that holds it up."
The Public Health Community
Non-governmental organizations (NGOs) and global health advocates have raised alarms regarding the $7.3 billion shortfall. Groups like Doctors Without Borders and the Global Fund have warned that if domestic co-investment fails to materialize—due to economic downturns or shifts in local political will—the progress made against HIV and Malaria over the last two decades could be reversed.
Implications: A High-Stakes Gamble on Self-Reliance
The shift toward the America First Global Health Strategy carries profound implications for the future of international relations and public health.
1. The Risk of "The Gap"
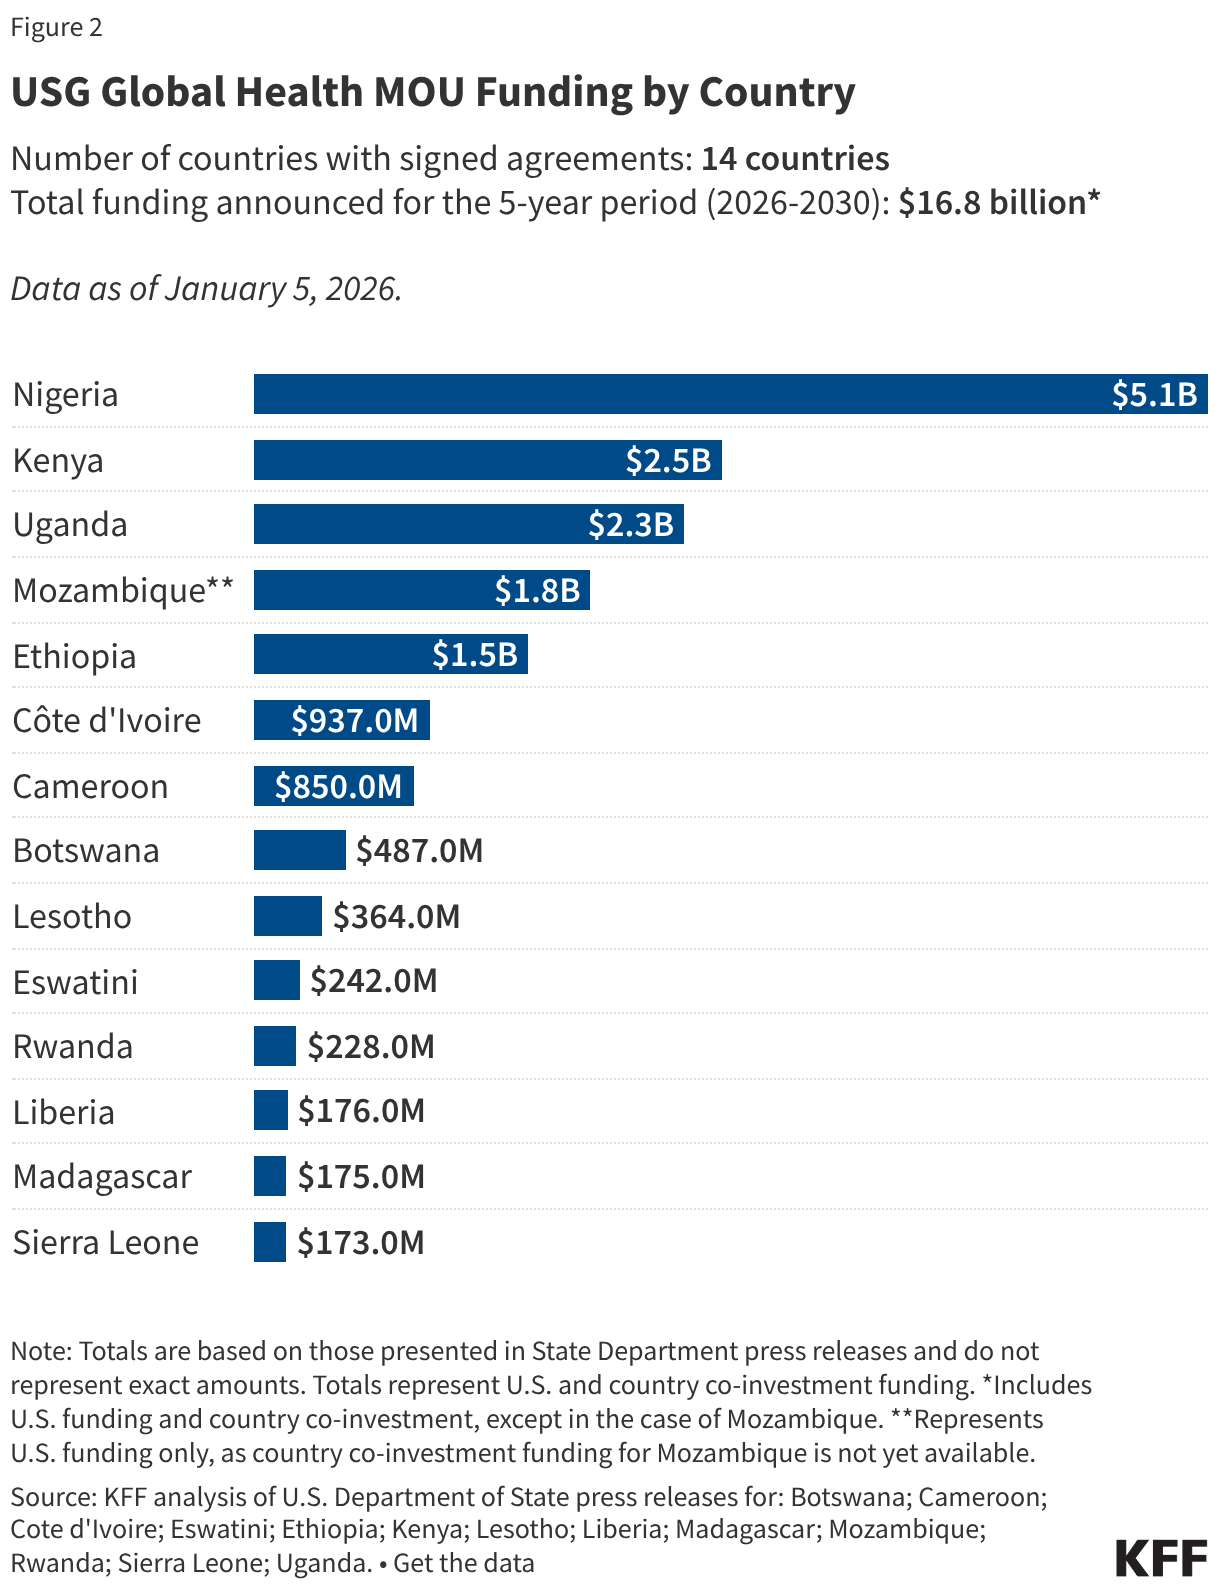
The primary concern is whether partner nations can actually fill the $7.3 billion void. In many of these 34 countries, the health budget is already stretched thin. If domestic spending does not increase as pledged, essential services—such as vaccine distribution and infectious disease monitoring—could collapse.
2. Geopolitical Shifts
As the U.S. reduces its financial footprint, a vacuum may be created. Observers suggest that other global powers, including China and the European Union, may move to fill this space with their own health diplomacy initiatives, potentially shifting the geopolitical alignment of these 34 nations.
3. A New Model for "Global Health Security"
The strategy’s heavy emphasis on Global Health Security (GHS) suggests that the U.S. is prioritizing "defense-style" health spending. By focusing on outbreak preparedness, the USG is essentially treating global health as a border security issue. If successful, this could create a world where countries are better equipped to stop pandemics at the source. If it fails, the lack of general health funding could weaken the very systems needed to detect those outbreaks.
4. The End of the "PEPFAR Era"
For twenty years, the U.S. was the undisputed leader in global health through massive, direct-service funding. The 2026–2030 MOUs signal the end of that era. The success of this strategy will be measured not by how much the U.S. gives, but by how effectively it can stop giving without causing a systemic collapse.
Conclusion
The America First Global Health Strategy is a bold, albeit controversial, attempt to redefine international aid. By the end of 2030, the global community will know if this "Great Transition" succeeded in creating self-reliant health systems or if it merely signaled a retreat that left the world’s most vulnerable populations at risk. For now, the 34 signed MOUs stand as a testament to a new American philosophy: health as a shared responsibility, but a domestic burden.
Methods Note: This report is based on KFF analysis of U.S. Department of State, U.S. embassy, and partner country Ministries of Health press releases and MOU documents. Funding data represents Global Health Programs (GHP) accounts and does not include separate emergency appropriations or private sector contributions.

